Where is the Love for LADA/Slow Progressing/Early-Stage Type 1 Diabetes?

I was recently at the Annual Meeting for the European Association for the Study of Diabetes, known as “EASD”. This is the largest diabetes conference in the world (this year around 16,000 attended) and only rivalled globally by the America equivalent, the Scientific Sessions of the American Diabetes Association, the “ADA” which typically gets around 12,000 attendees.

One of the big announcements was an updated consensus guide for the management of type 1 diabetes. The previous consensus guide came out five years ago which I had merged with Buzzetti et. al.’s international consensus for the management of LADA to create an “all in one” guide for the diagnosis and treatment of someone with type 1, type 2, or LADA.

I was interested to see where LADA (“latent autoimmune diabetes in adults”) stood in the scientific consensus, given it is part of type 1, and how the guide considered its management.

What is LADA?

The 2021 version of the consensus guide did not make a strong stand on LADA saying “Controversy remains as to whether latent autoimmune diabetes of adulthood (LADA) is a discrete subtype, a milder form of type 1 diabetes, or a mixture of some individuals with type 1 diabetes and others with type 2 diabetes”. The last option came from a study where it was concluded there was enough false positive results in people with type 2 being misdiagnosed as type 1 to explain those who believe they are LADA.

Being considered a misdiagnosed type 2 (which I had been accused of on social media) was annoying and I personally discount this possibility from my own experience; I have been tested for autoantibodies on three separate occasions, all positive and yet I only needed insulin five years after diagnosis (my HbA1c had crept up to 6.8% which was, for me, too high). I am clearly autoimmune (type 1) and slow progressing and not a “false positive”.

Thankfully, the 2026 version improves on this and defines LADA as “…adults with diabetes who have islet autoantibodies but do not initially require insulin therapy.” They then give a stronger position saying “LADA represents a spectrum of type 1 diabetes, rather than a distinct subtype, characterized by slower β-cell loss than in children with type 1 diabetes and variable progression to insulin dependence.”

So, the guideline is now clear that LADA:

  • Does not initially require insulin
  • Part of a spectrum of type 1 diabetes which spans fast progressing (type 1 diagnosed in childhood) to slow progressing in adults (the ‘LADA’ end)

Where Does LADA Fit in?

So now LADA is considered part of the broad church of type 1 diabetes, how does it reconcile with modern models of type 1 progression?

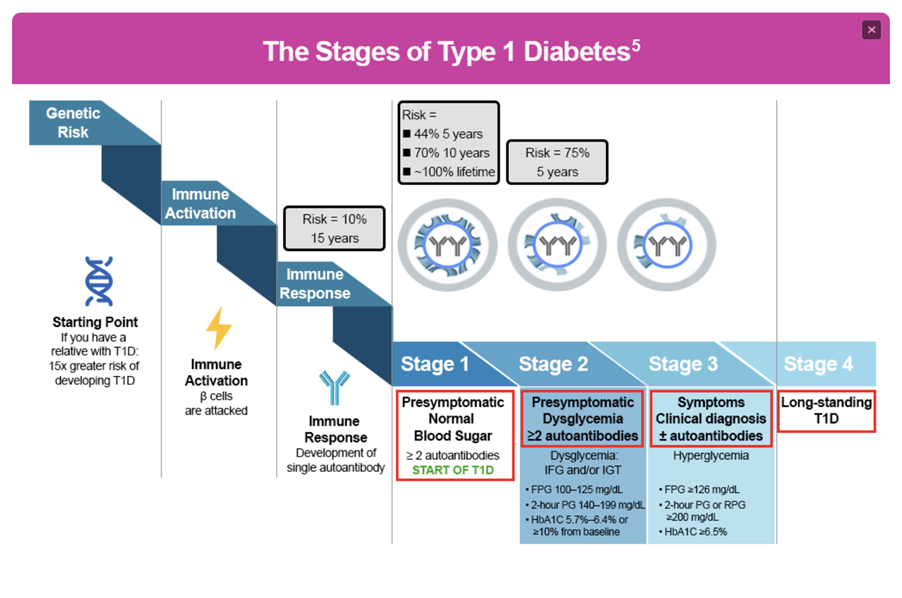
The 2026 guide referred to the staging model of type 1 diabetes but did not have a picture showing it. The one below is sourced from detect-t1d.com

When I was diagnosed with diabetes I had three of the four T’s (Thirst, Tired, Toilet, Thinning). My HbA1c was 9.6%, and my fasting blood glucose was 259 mg/dL (14.4 mmol/L). No Thinning but the rest of the ‘T’s were there and my blood results were out of range across a wide variety of measures. While initially misdiagnosed as having type 2 diabetes, when the autoantibody tests were conducted, I was positive for the three antibodies tested (GAD, Zinc Transporter 8 Abs, IA-2). This puts me in at least Stage 2, given the ‘T’ symptoms.

From 2017 (initial diagnosis) to 2019, my HbA1c was in the normal reference range (<5.6%), managed through diet and some exercise. From 2020 to 2021 it remained below 6.5% and, as mentioned, when it hit 6.8% in 2022, I went on to insulin and it came back down again. Interestingly, my fasting blood glucose (FPG) also remained below 125 mg/dl (6.9 mmol/L) until 2022.

Based on the above data, and comparing to the figure, it seems I was in Stage 2 from 2017 through to 2021 and then progressed to Stage 3 in 2022. So, it is possible to overlay LADA onto the stage model if we acknowledge that interventions, such as diet and exercise, can put us into ‘earlier stage remission’, at least temporarily.

Guidance for Managing LADA/Slow Progressing Type 1 Diabetes/Early-Stage Type 1 Diabetes

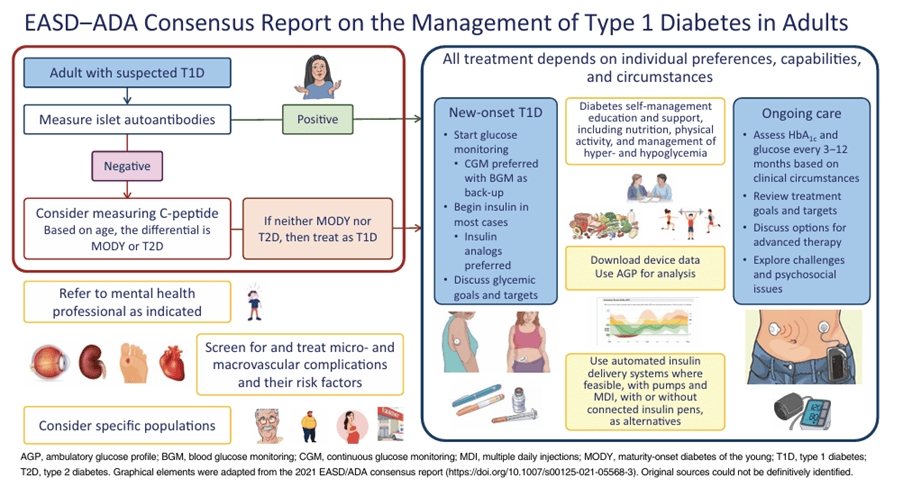
The first guide for management in the consensus guide is the initial diagram.

Considering an antibody-positive person with LADA, we end up at “New-onset T1D” with the recommendation of “begin insulin in most cases”, which we know, by definition, excludes LADA. The recommendation is also to assess HbA1c every 3-12 months. This is a vague cadence and, given people with LADA are not going to be on insulin, potentially dangerous because of the risk of DKA. The guide acknowledges the risk saying “Adults with new-onset type 1 diabetes are frequently misdiagnosed as having type 2 diabetes, leading to delays in insulin treatment and an increased risk of diabetic (ketoacidosis).” so it concerns me the initial figure is vague on this aspect for all except ‘classic type 1s’.

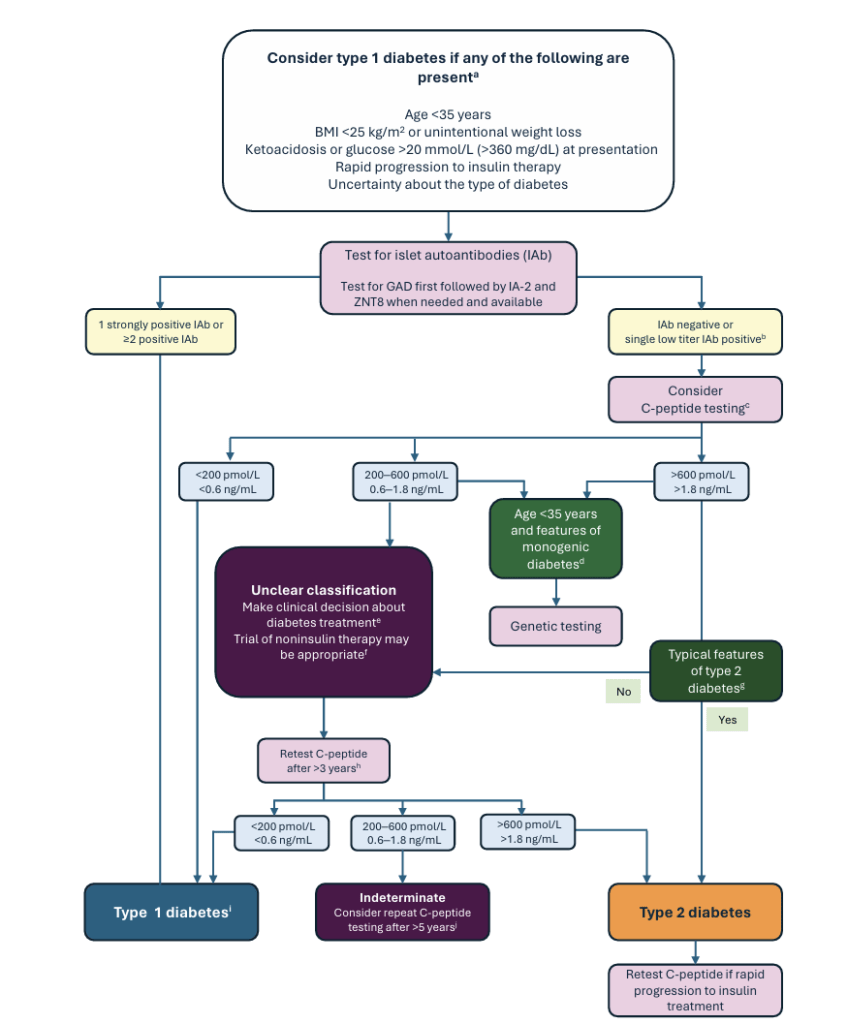
Fortunately, further into the document is a more detailed flow chart for diabetes type diagnosis.

On this one, my personal version of LADA did NOT meet the initial box. I was 42 years of age at presentation, my BMI was higher than 25, while I did have ketones in my blood, I had also been fasting for more than 12 hours so the hospital decided they were ‘fasting ketones’ and not ‘DKA ketones’. Given this was the case, they chose not to do autoantibody testing and sent me away as a person with type 2 diabetes. It was my family doctor who ordered the tests a couple of weeks later, reclassifying me as having type 1 diabetes.

I contend that the initial box on this diagram may hinder accurate diagnosis of people with LADA/slow progressing type 1 diabetes, rather than help, and should be removed. However, assuming we move past the box, my autoimmunity immediately puts me into the type 1 diabetes classification.

Interestingly, the use of c-peptide as a measure for differentiating type 1 diabetes may also be problematic. In my case, up until the use of endogenous insulin, my c-peptide was in the upper end of the range or even above it (2.2 ng/mL in 2020, three years after diagnosis), presumably due to insulin resistance.

The only time my c-peptide has been below 0.6ng/mL was when I began using insulin which, of course, supressed my body’s production. A stimulated c-peptide test I did, in 2024, yielded a result of 1.71 ng/mL meaning seven years on from diagnosis I still had insulin production, contradicting (or, at least, not supporting) the guide’s claims that “C-peptide levels…are usually low or undetectable by 3 years after diagnosis.”

I mentioned earlier the vague cadence recommended for follow-up and, even though, there is an entire sub-section explaining the stages of type 1 diabetes, there are no specific recommendations for an early-stage management cadence. The stages section talks about screening to identify people at Stage 2 Type 1 diabetes but, the fact is, diagnosis of LADA/Slow Progressing Type 1 Diabetes, gives another avenue for finding people before they reach Stage 3 with none of the downsides and risks of screening. For these people, the consensus guide should provide advice on management, including measures to minimise the risks associated with transitioning to Stage 3 and a well-defined cadence for consultation/testing.

While understandable, the guide is insulin-centric in terms of its management of type 1 diabetes. With LADA/early-stage type 1 diabetes not initially requiring insulin, literally by definition, this means the guidance is not as robust as it could be for this cohort. The section on Diabetes Self-Management Education and Support (DSMES) assumes ‘Medication usage’ is exclusively insulin in its key content areas. The ‘Content areas of DSMES’ similarly speak of ‘Insulin types and administration’ but do not mention adjunct therapies.

The section on “Interventions to Manage Glucose Levels” immediately states “ Lifelong insulin therapy is essential in type 1 diabetes and should be personalized to optimize glycemic levels.” which may be true in the long-term but not true for slow progressing forms of type 1 diabetes and early-stage type 1 diabetes. We also see this in the next section on “Adjunctive Therapies for Glycemic Management” which states “…insulin therapy is essential for people with type 1 diabetes…”. It may be better to rename the guide “The Management of (Stage 3) Type 1 Diabetes in Adults…” given its focus on insulin dependence and rapid onset and with the only clear guidance for Stage 2 Type 1 Diabetes management being the use of immunomodulatory drugs such as Tepliumab.

Why Should We Care About LADA?

An argument could be made that adjusting the entire guide to account for a diabetes population which is “10% of people with type 1 which itself is roughly 10% of all people with diabetes” in unnecessary. However, it is estimated that between 6-50% of people with type 2 diabetes are, in fact, people with LADA. This makes the cohort of people with undiagnosed LADA of a size comparable to the entire diagnosed type 1 population and, therefore, worthy of consideration, especially as the guidance will also serve people identified with Stage 2 Type 1 Diabetes through screening.

How Can We Improve the Guide?

Given it was five years since the last update to the guide, it is unlikely the guide will be substantially changed in the near-term. However, we can summarise those areas for improvement with a view of including them in future releases. Specifically:

  • Determine if the guide is specifically for Stage 3 Type 1 Diabetes or, more broadly, includes earlier stages and slow-progressing forms
  • Assuming earlier stages are included, acknowledge that the management for type 1 diabetes in early-stage and slow-progressing forms do not necessarily involve endogenous insulin
  • Give unambiguous guidance for the cadence of monitoring Stage 2 Type 1 Diabetes to minimise the risk of DKA on progression to Stage 3
  • Modify the diagnosis flow chart to account for early-stage and slow progressing forms of type 1 diabetes, rather than excluding the possibility of autoimmunity. This may include elements such as genetic screening or classification models such as those of the University of Exeter.

By considering type 1 diabetes prior to Stage 3, we shift the focus from simple diagnosis of Stage 3 to progression to Stage 3, and the inclusion of management of Stage 2 and slow progressing forms. The guide becomes relevant to many more people on the journey of type 1 diabetes and the health care providers working with them.

Review: VIVI Cap Smart

A few months ago, I compared the VIVI Cap to the InsulinSaver bag. While the InsulinSaver bag proved to be more robust at keep the insulin at temperature, I can see scenarios where the VIVI Cap could prove useful e.g. when you cannot carry a bag. As the form factor is essentially the same with the VIVI Cap Smart as the VIVI Cap, I will not do a Insulin Cooling Battle, but I will explore the extra features it comes with. As with the previous review, Tempramed gave me the device for free to review but gave no guidance on what I could or should write. The review below is wholly my own opinion.

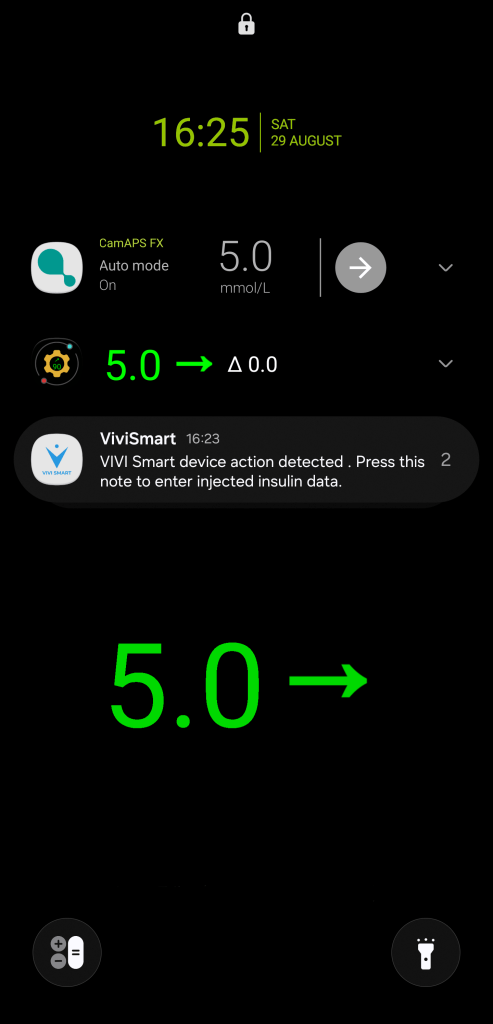
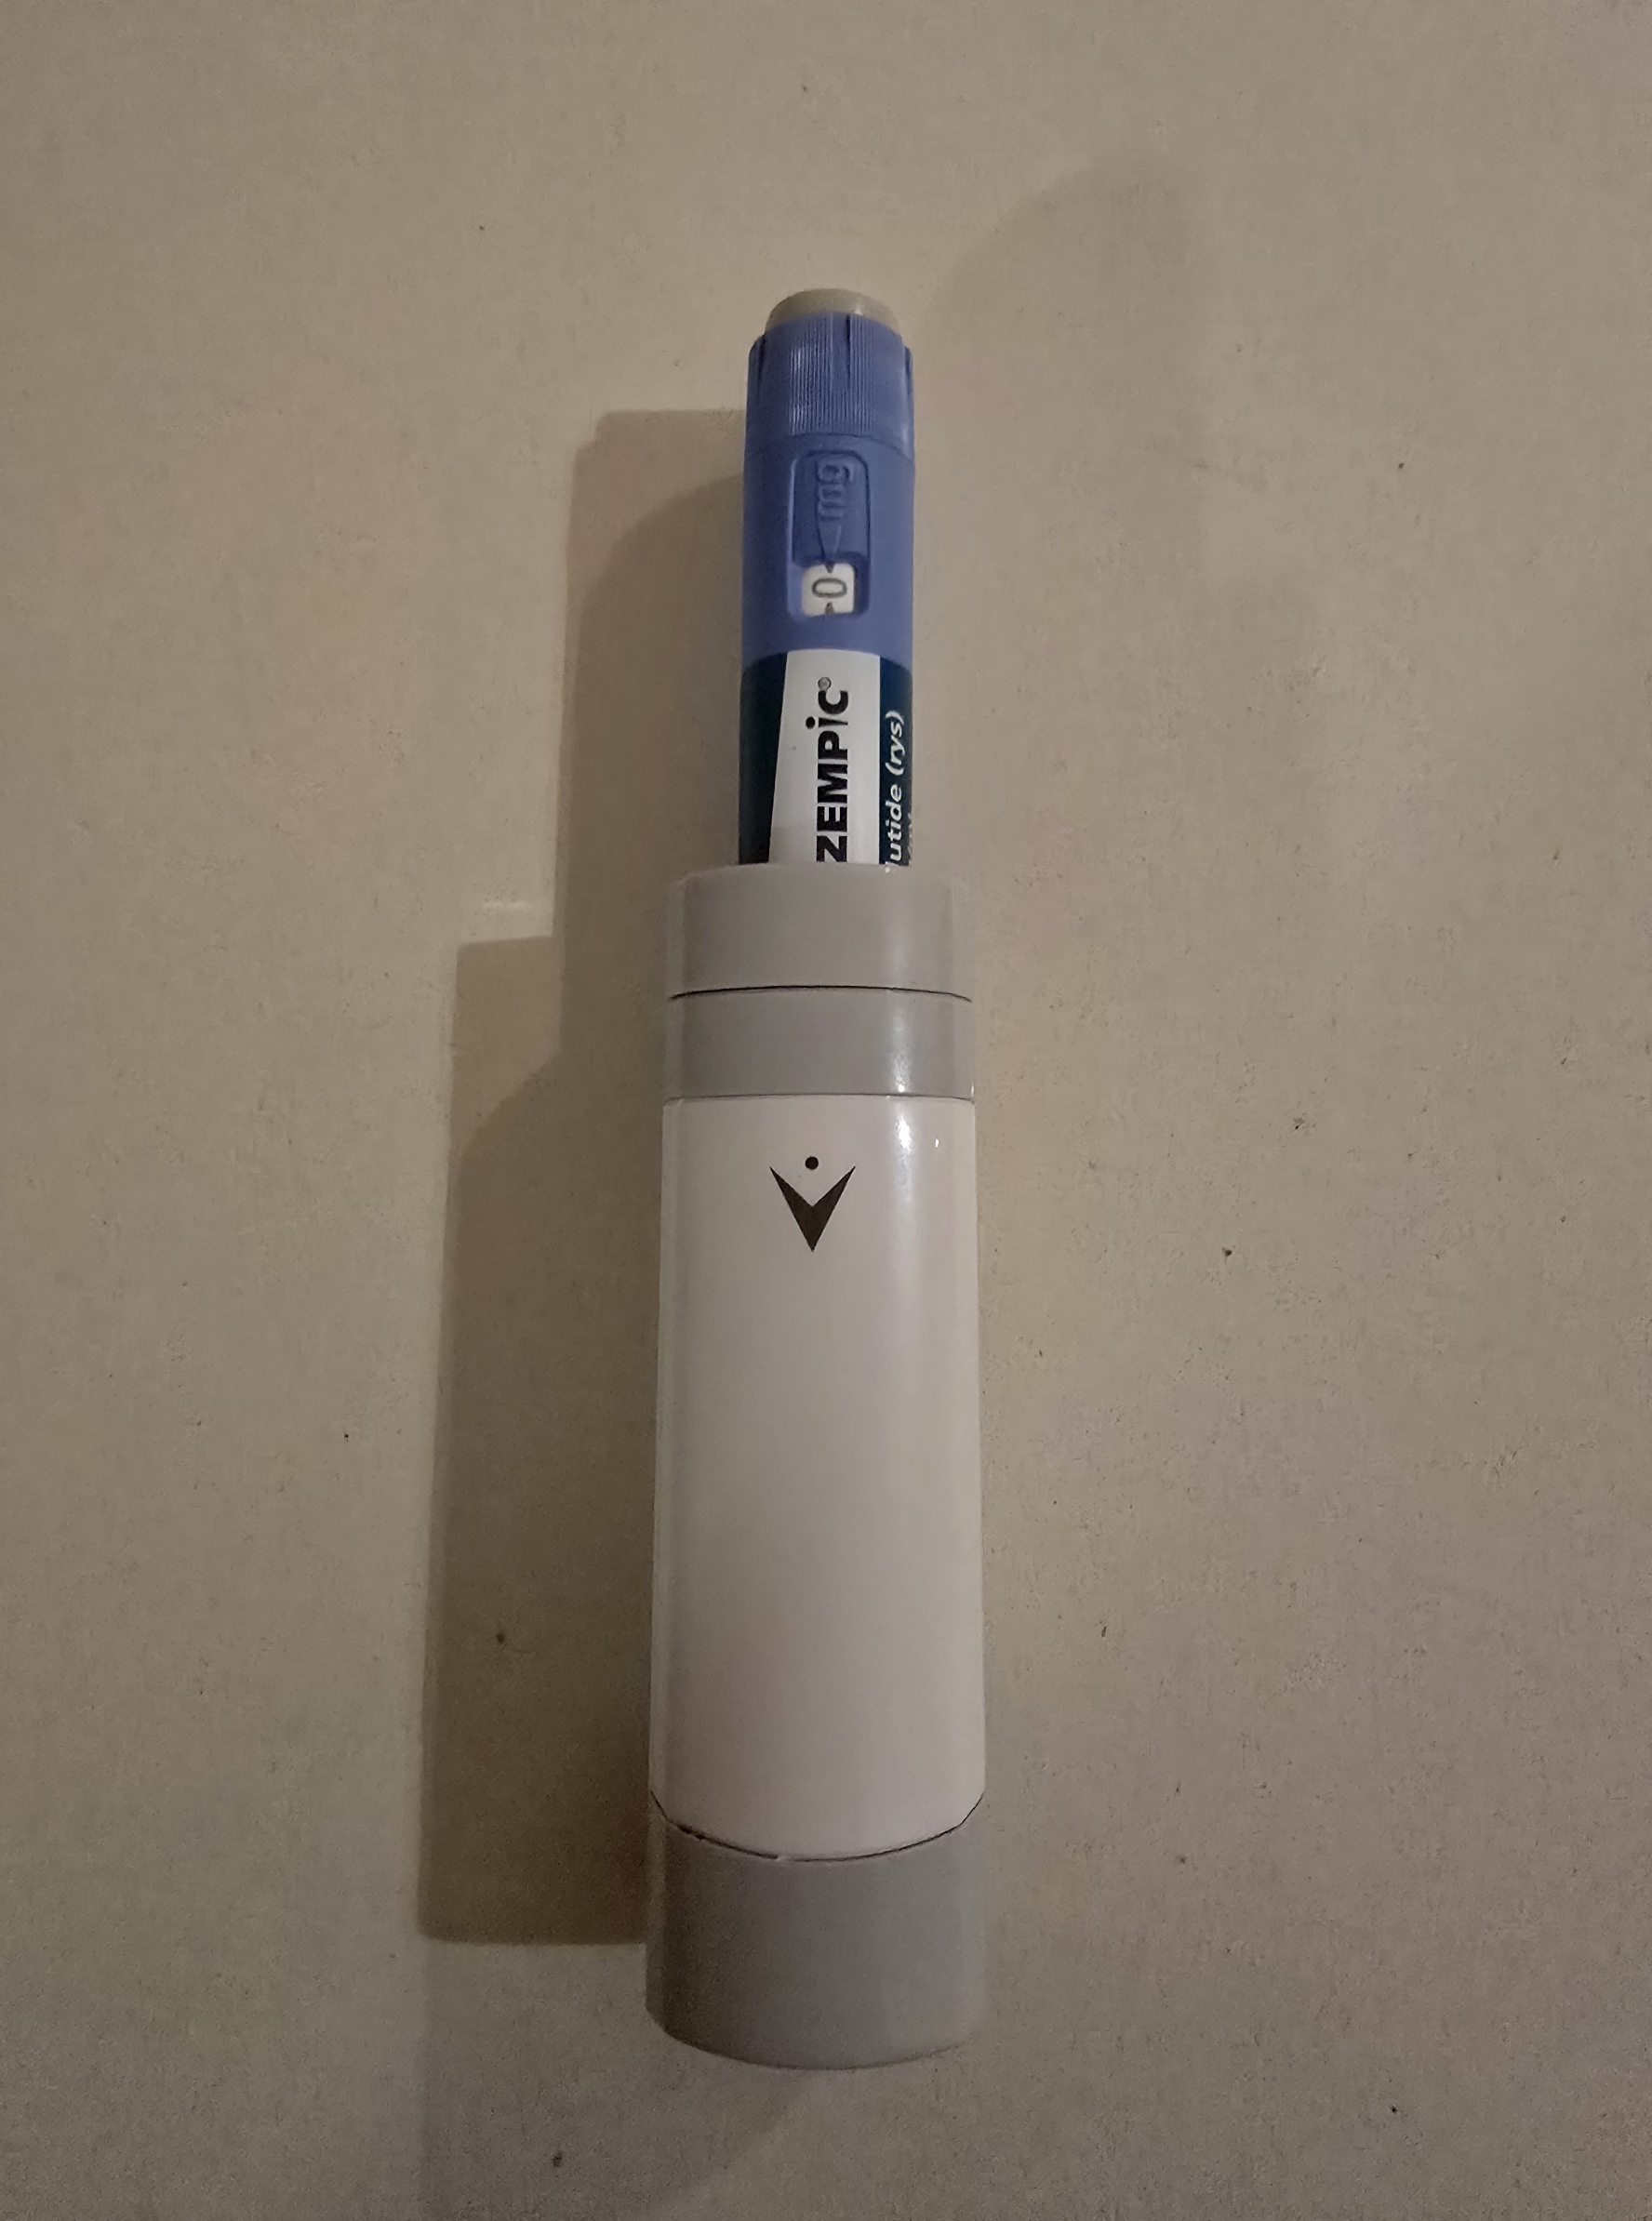
The key difference between the VIVI Cap and the ‘Smart’ edition is the inclusion of an opening sensor. This keeps track of when the case is opened and links to the ViviSmart app on your phone (Apple or Android) via Bluetooth so you can record the details of your injection. My guess is there is a proximity sensor in the top of the cap so when the cap is removed, it no longer sees a pen and records the opening. This makes me wonder whether it would still work with a shorter pen such as the older red Ozempics. The app is very useful at reminding you to record it as well, putting up a notification on the phone when a cap removal is detected and putting a placeholder entry in the app, ready for completion.

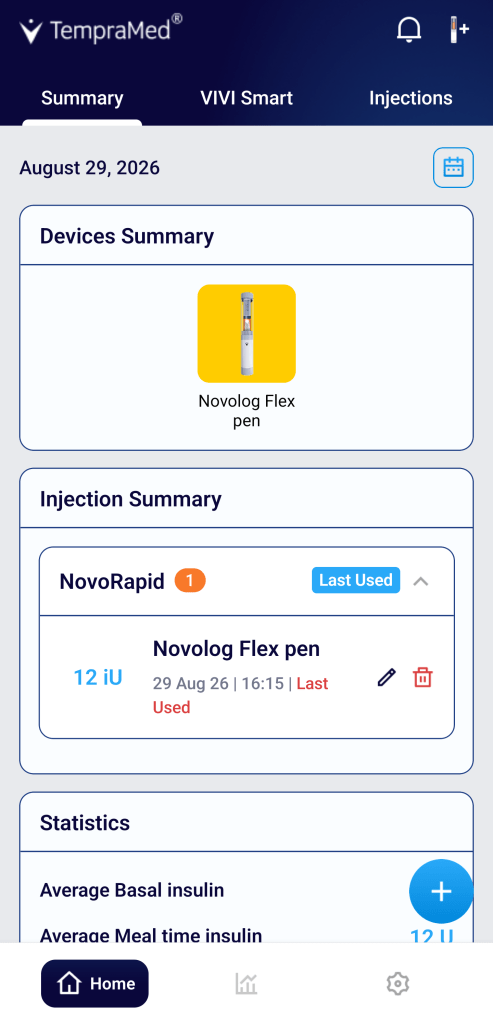
Sure enough, if you click through on the notification, the app opens up and lets you record the injection.

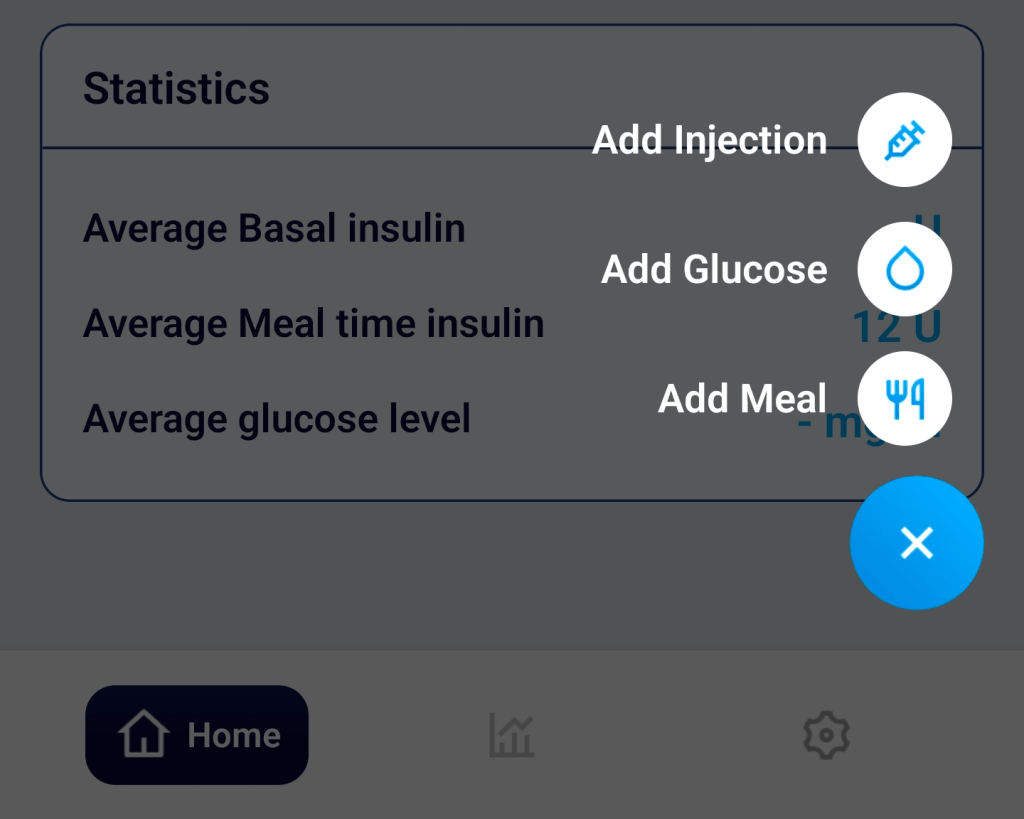
You can also record your BGL values manually, and meals.

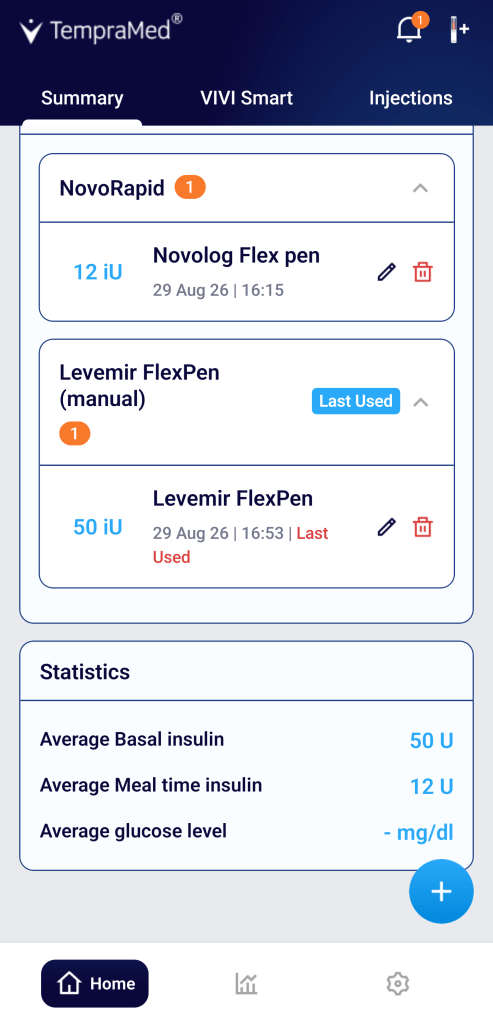
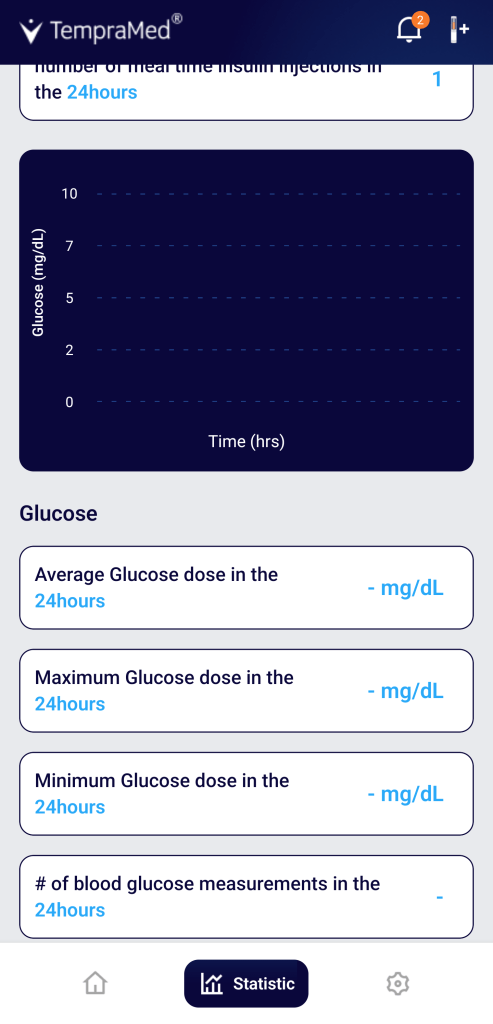
The other two tabs in the app (VIVI Smart and Injections) are essentially summaries of the data you have recorded. VIVI Smart tells you the pens you have used and Injections gives you a timeline of what you have done with them.

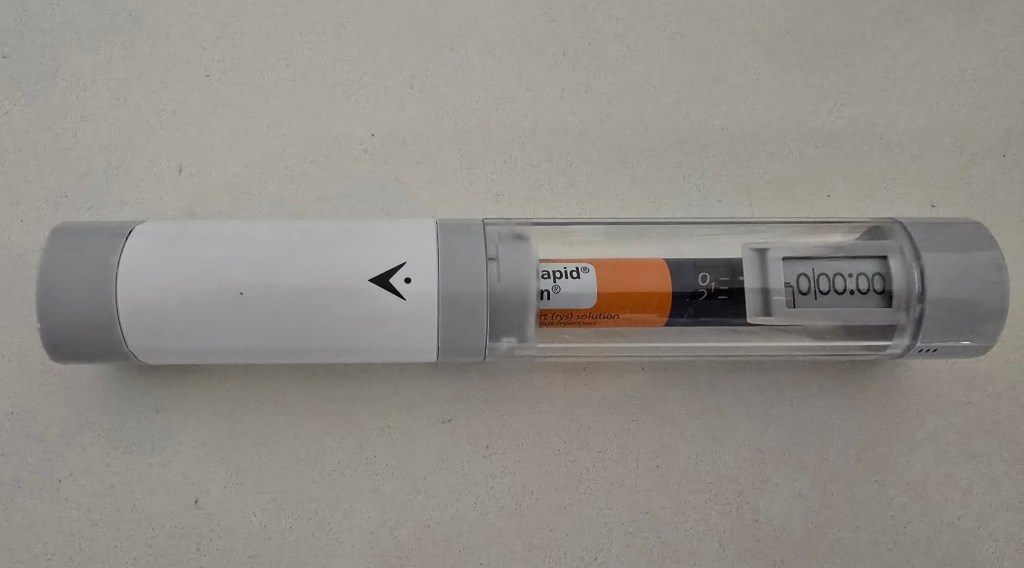
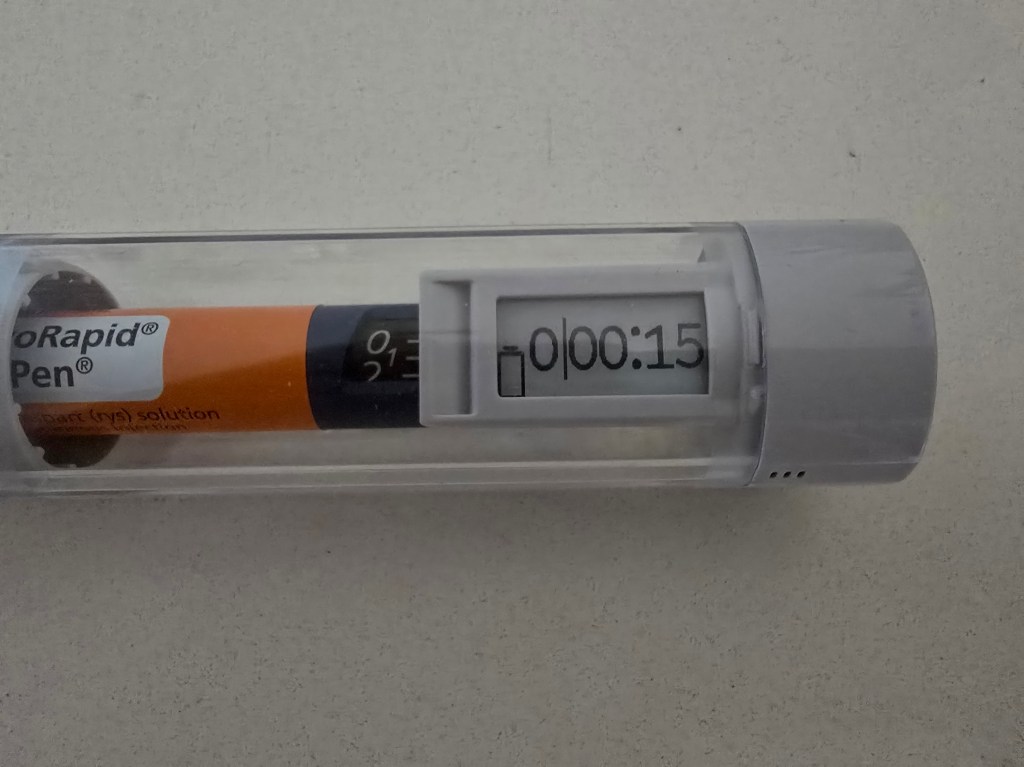
On the cap readout, it tells you how long ago (in days/hours/minutes) since you last opened up the VIVI Cap and how much charge the battery has. In the image below, 15 minutes. The battery is very, very hardy so you do not need to charge it often (the pen has been sitting by my chair for a few weeks and the readout was still going strong). One word of warning, the display maxes out and freezes at 9 days, 23 hours and 58 minutes so if you plan to keep the case closed for longer periods than this, the display will not tell you how long it has been.

In terms of the physical device, it is otherwise the same as the VIVI Cap. The key differences are in the app.

The VIVI Cap Smart app

While I only had the opportunity to work with one VIVI Cap Smart, you can link multiple devices to the one app, if you have multiple VIVI Cap Smart cases. Although, if you are simply maintaining the temperature of the pens, unless you need the smart features, there may be value in considering a bag like the InsulinSaver or BreezyPacks bags instead.

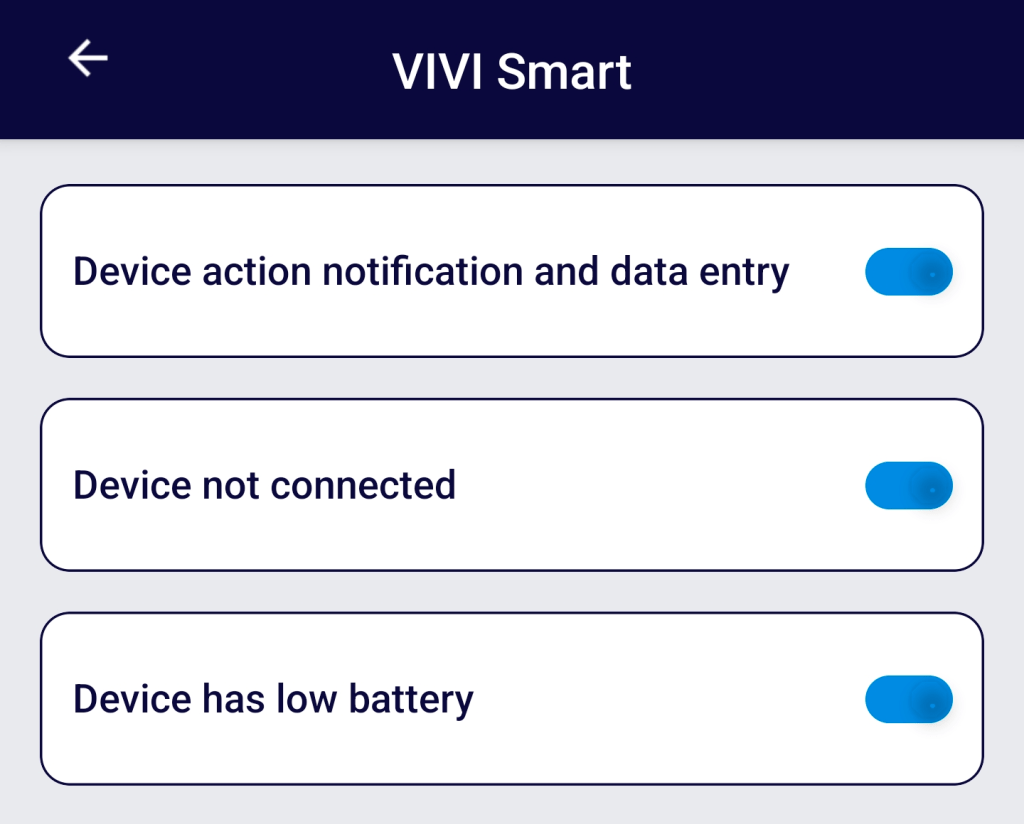
A feature mentioned on the box was the ability to receive notifications and reminders. This can be found in the Settings area of the app. Some are behind a paywall (I will get to that later) but the ones which can be accessed for free are for the insulin pen and the VIVI Smart container. For the insulin pens, there are no settings to say how old is too old for the insulin so I assume it uses the manufacturers’ recommendations.

I was also wondering how it knew what injections were for bolus and which for basal. From what I can tell, it uses the type of insulin selected when the injection is recorded. So, for example, if I inject Levemir, it assumes this is for a basal injection whereas Novorapid is for meals.

There is also the ability to export your data in the Settings area which I like. It is your data and you should have the right to pull it out and do as you wish with it. Formats for export are PDF and CSV.

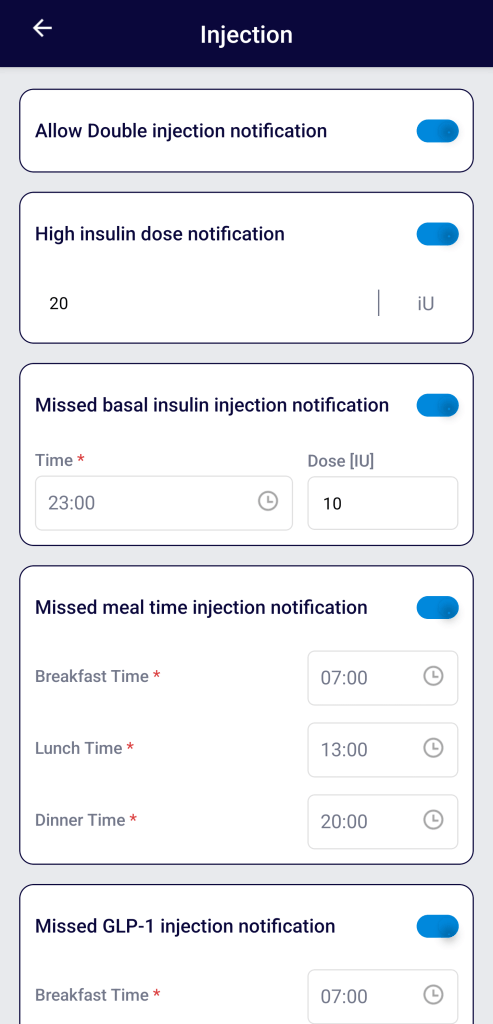
The additional features of the app sit behind a paid feature called Smart+. For the purposes of review, I requested access so I could cover it. Basically, Smart+ gives you some additional notifications and some statistical analysis of your data around insulin use and BGL levels. Here are the additional notifications/reminders:

I was not overly impressed with the layout here, specifically around the time selection. In some cases, people do more than one basal injection per day (or in the case of insulin icodec, they do it once per week). The idea of fixed mealtimes is also problematic, at least for me, although I do not have a good solution for how to get around this and still maintain useful notifications. The assumption that GLP-1s are only injected at breakfast is also problematic but this value is independent of the other breakfast value in the missed mealtime area so, if you inject your Ozempic at dinner time or before you go to bed, you simply set the time to match, ignoring the field label.

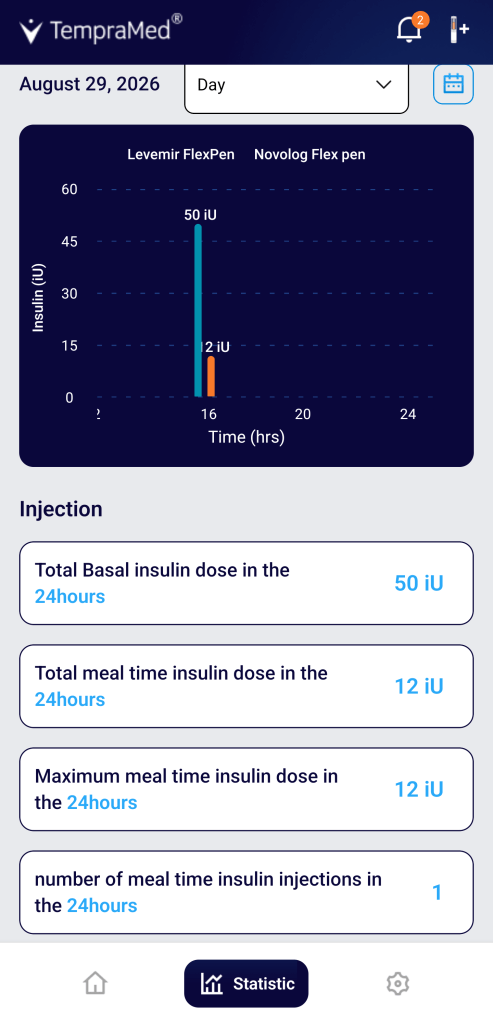
Here is the statistical analysis provided. A little surprising was the lack of temperature data which, presumably it is capturing for the light on the bottom which changes colour when the insulin pen is too hot.

I could not find too much online on how much the Smart+ subscription costs but, given you can export the data, if you have a Sheets/Excel guru friend who works for pizza slices, perhaps they can help set up something similar.

Other Stuff

While using it for the review I did make note of some other ‘features’ as I went along such as:

  • I could not get the provided charging cable to work at all. However, the VIVI Cap Smart did charge off of other USB-C chargers so this was not a showstopper. The way you know if it is charging or not is that there is a tiny red light next to the charging port which comes on when it is charging.
  • The moment you start charging the VIVI Cap Smart, it will reset the device (not the app). This means it will forget the time since the last injection and immediately reset the clock back to 0.
  • I had made a note that, in the profile section you could only put yourself down as type 1 or type 2 leaving out a variety of other options. What is strange is that when I went back to the Profile section of the Settings to revisit this, I could no longer access it; the additional Profile areas, for some reason, were inaccessible through the app and all I could access was the first part.
  • When setting up the Bluetooth connection between the device and my phone I could not match the serial number to the name given. It just meant I had to take it on faith it was the correct device.
  • The card insert which comes with the device has very small text. For people with sight impairment of any kind, this will be tricky. There was a QR code for the user manual on there which worked and was useful in understanding some of the device’s aspects.
  • There is a feature to record insulin amounts via voice, rather than type it in, although it is quite limited. Perhaps it is my Australian accent, but I found it struggled to record values. It simply did not hear them, even when the microphone icon was clearly visible. You could not use the voice command to set the insulin pen you used so this still requires touching the phone. Also, it would be nice to have this feature for recording BGLs and meals, not just insulin amounts.

Conclusions

Overall, for people doing daily multiple injections, this has some nice smart pen features with the added benefit of helping maintain a safe temperature for the medication it contains. There are some peccadillos, as mentioned above, but, if you need something to hold a pen where a small bag is not going to work and notifications/reminders are useful, this could be a good addition to your inventory and, I believe, provides a lot more ‘bang for buck’ for an additional US$20 over the non-smart VIVI Cap.

Insulin Cooling Battles: VIVI Cap vs InsulinSaver

For my previous cooling battles see:

This time I am testing the VIVI Cap which TempraMed kindly sent me in exchange for a review. Their only guidance for the review was, given they have sent me the VIVI Cap, the VIVI Cap Smart, and the VIVI Med, they asked I do one article per device. Other than being able to keep the devices, no other incentives were given.

What is the VIVI Cap?

This is the VIVI Cap:

Inside you get an instruction card, an offer for a free discount on your next TempraMed purchase, the cap and a transparent case or collar for the top.

Essentially, it is a device which replaces your pen cap and attempts to keep the insulin below 30C (86F). The devices fits a variety of pens. I tried it with a FlexPen (NovoRapid), FlexTouch (Ozempic) and a KiwkPen (Mounjaro) and all three worked fine. It also has a button on the bottom you can press to confirm “insulin temperature below limit” with a green LED light giving the all-clear.

How Does it Work?

Like the InsulinSaver Bag and BreezyPack bags, it uses a Phase Change Material (PCM) to absorb excess heat and keep the insulin at a safe temperature. On the instruction card it says the threshold temperature is 26C (79F). This does not directly match the melting point of paraffin waxes such as octadecane so I am unsure what PCM is being used.

To understand why the PCM is so useful in this application, we need to recap a bit of science. As you may remember from high school science, matter has three common phases (gas, liquid, and solid). What you may not have been taught is that as you heat something, when it reaches the boundary between two phases, the heat is still absorbed by the material but the temperature stays the same. If we think of boiling water, it does not matter how much heat we apply, it will never go above 100C (212F). Instead the excess heat is turned into steam. More interestingly, it takes more than 5 times the heat energy to move the water from 100C to 100C and boiling, than it takes to get it from 1C (34F) to 100C.

PCMs work the same way. At their threshold temperature, they stop getting hotter and start melting, until they are completely liquified.

As a side, note, the Frio uses the same principle, but, in its case, the phase change is water going from liquid to gas i.e. evaporation. The advantage PCM-based solutions have is no need for soaking with the material ‘recharging’ when the temperature gets low enough for the material to re-solidify.

How Does it Compare to the InsulinSaver?

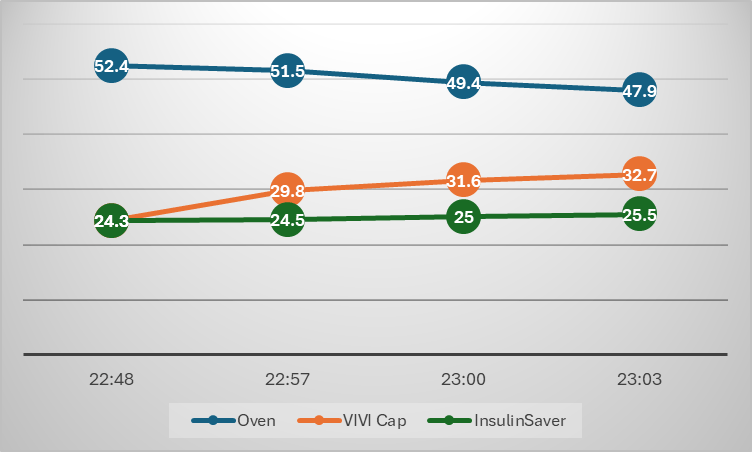
Unfortunately, it did not do so well. I used my usual set up of temperature probes embedded in the insulin reservoir on an insulin pen.

Two of these were put in a VIVI Cap and Insulin Saver and a third probe was used to measure the temperature of the oven.

Placing the two items in the oven we get the following temperature movement.

In short, the VIVI Cap struggled at 50-ish C (122F). More worryingly, even when the probe temperature was beyond 30C, the light was still registering green.

Now, to be fair to the VIVI Cap the instruction card does say “it is intended to keep insulin within safe temperatures below 84.2F (29C) for minimum 12 hours even in a constant environmental temperature of 100F (37.8C), when the device is placed inside a personal handbag.” Clearly, putting it in an oven running at 50C was outside this range. My guess is the temperature sensor is in the bottom part of the VIVI Cap and the rapid heating had not allowed for the increased temperature to reach the green light sensor.

Also, as we learned from the InsulinSaver vs BreezyPack comparison, the amount of PCM material has some correlation to the device’s ability to resist temperature change (more material to melt means longer protection so this makes sense). There is not a lot of PCM material in the VIVI Cap (Cap weight is 70g vs InsulinSaver’s 368g) so it was unlikely to keep up under these conditions.

At US$140 for one VIVI Cap vs US$43 for the InsulinSaver Bag/Breezy Extra it is worth considering whether you want to spend the extra for some protection and a slimmer profile or buy the chunkier bag (which can hold multiple pens).

For me, I can see someone using it when they need to carry an insulin pen but space is of a premium or they simply cannot carry a bag with them and they are going to be exposed to high temperatures e.g. swimming or diving, rock climbing, cross-country or long distance running, construction workers, factory workers, or kitchen hands.

My next review will be for the VIVI Cap Smart which is a similar device but pairs with an app to track injections.

My Diabetes Bug-Out Bag

I have written before about my Diabetes Day Pack and What to Pack When Travelling on a Plane. A lot of this is now contained in my Bug-Out Bag which acts as a Day Pack (when I go to the office, work on site etc.) as well as a Carry-On bag for flights.

Why a Bug-Out Bag?

Before I had my diabetes bag which was exclusively for diabetes stuff but the new bag combines work gear as well. This makes sense for me as the main reason for leaving the house during the week is work and it is also the main reason why I fly interstate. Whereas before this would mean hauling two bags with me (a laptop/work bag and my diabetes bag) this is now all in one. It also makes spontaneous travel a lot easier as I simply pick up the bag and I am good to go.

The Anatomy of my Bug-Out Bag

The key elements are:

  • Large enough to fit all your stuff in but small enough to slide under the seat in front of you when on the plane. My bag is at the upper limit for under seat storage
  • Two sections: one for work and one for diabetes stuff. This makes life a lot easier when finding things and, if the airline takes exception to the weight of the bag, it is easy to find the ‘medical supplies’ for weight exemption or for moving them into your check-in bags (with the possible exception of insulin and other essential supplies)

A nice feature of this particular bag is it folds out into two parts and has a transparent window on one of them. This is useful for showing needles and other ‘restricted’ items although I rarely have to use it.

Contents of the Bug-Out Bag

I will break it down into three areas:

  • Work area: Laptop, papers, power bank, cables etc., the usual stuff a tech professional carries around
  • Side pouches: Small pockets on the front which I will go through in detail below
  • Diabetes area: Where the diabetes stuff is which I will also go through below

Side Pouches

As can be seen in the photo, I have a water bottle on the side of the bag. Always useful when at the airport gate and for making cold brew tea in hotel rooms but, in this case, it is also useful as an insulin case, if needed. Not only is the bottle insulated but it has a temperature gauge on the top. Fill it with fridge water, put your insulin reservoirs/vials in a ziplok and you can store them in there for literally hours in any weather and they will be completely safe. I picked this one up on Temu a few years ago for A$15 and it has served me well ever since.

My first zippered side pouch has the following items.

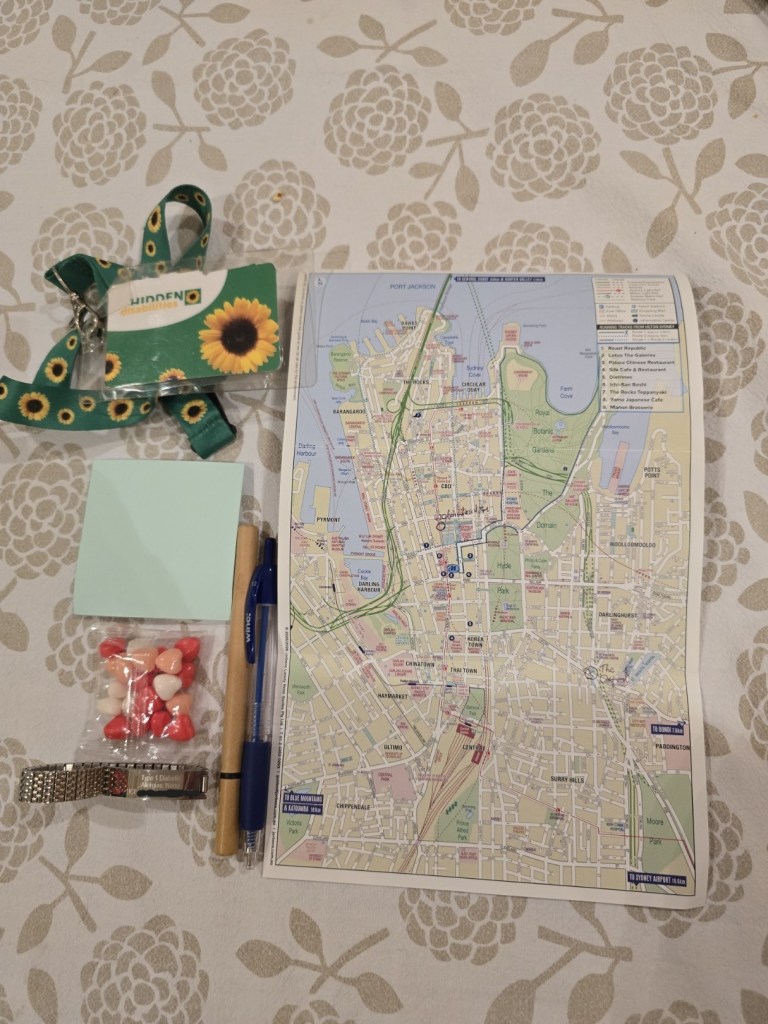
Here we see:

  • Hypo-candy
  • Post-It notes and pens: Always useful and you can make origami out of the square Post-Its when bored at the gate to entertain fellow passengers. Always have at least two pens so if one runs out you have a backup. Although it is becoming increasingly rare, if you need to fill out forms or arrival or departure, black ink is your safest option.
  • A map of the local city: These can be picked up for free at most hotels and, for me, are super useful. I used to carry interstate maps for excellent cocktail bars but, as they come and go quite frequently, I find Google Maps to be more reliable these days. I use this map for places in the city where I can work between meetings. It is a relatively new map so not many places yet. You could also use it for public toilets, chemists/pharmacies, medical centres etc.
  • Sunflower lanyard: Not very useful day-to-day but I always wear it at the airport. While it confers no inherent perks or privileges, it does indicate to staff you may take a little longer going through screening (I always request a pat-down as my pump is not certified for the scanners) and may have individual needs boarding. Wearing the lanyard has given me access to the priority queue for security and priority boarding in multiple countries. Priority boarding is useful when I have two carry-on items and want them nearby in flight. Sunflower lanyards can be picked up at participating airports/train stations/malls so check online for somewhere near you (https://hdsunflower.com/find-the-sunflower). In my experience though they are often out of stock. You can pick them up on Temu/Aliexpress/Shein for less than A$5 or from Amazon for A$10 or so.
  • Medi-bracelet: I do not often wear this but, if travelling in countries where my language skills are not strong, I sometimes put it on. In this case, it has my disease, my allergies and a contact “In Case of Emergencies”. This one I picked up on AliExpress, including engraving, for A$9.

In my second side pouch I have:

  • A pack of tissues (always useful for spills, blowing nose etc.)
  • A notepad with sage advice from Moominpappa
  • N90/P2 facemasks which I still wear on flights because people are animals and I enjoy not being sick when travelling.
  • Chopsticks: Emergency cutlery
  • Computer mouse
  • USB light: Very handy when changing pump sets in economy with the cabin lights off
  • Small powerbank: Easy to carry in a pocket and useful to keep the phone going in emergencies or for the USB light

Diabetes Section

That side section carries a lot of stuff with some of it in its own sub-containers for convenience.

We have:

  • My pump/CGM changing kit which contains
    • Nasonex spray which can be helpful if skin gets irritated by the adhesives
    • Pens and notebook: For capturing instructions for set changing procedures, passwords etc.
    • Safety razor: For deforesting a space to attach the cannula or CGM
    • Opsite patches: This is my current solution to the cannula adhesive. Basically, when I take a cannula off, I cover the site with Opsite. This does not relieve the itching/irritation but stops me damaging my skin when scratching the site. The irritation usually settles down after a day or two and I simply remove the patch. Opsite is a breathable plastic film which can be purchased at major chemists/pharmacies
    • Alcohol wipes: Used for wiping reservoirs/cartridges and skin when applying cannulas/CGMs
    • CGM Patches
    • Hand sanitising gel: For when I need to change my set but I do not have easy access to soap and water
    • AAA batteries: For my pump
    • Other bits for my set such as insulin transfer collar, cannula applicator etc.
  • MDI backup kit which contains
    • Prescriptions
    • Business cards of my health care team
    • A letter from my endo stating my pump and CGM cannot go through airport security
    • The slightly modified Bernstein pro-forma hospital admission letter advocating I continue to manage my levels in hospital and any saline bags used do not contain glucose or similar
    • Printouts of online web sites stating my devices cannot go through airport security scanners
    • Endo letter confirming I carry needles, insulin, juice etc. as a person with type 1 diabetes
    • Blood glucose meter and strips
    • Genteel pricker: If you still do finger pricks regularly, spend the money and get a Genteel. They are fantastic. Painless pricking, anywhere on your body, not just the fingertips
    • Splenda sweetener tabs for sugarless sweetening of foods
    • Ketone meter and strips
    • Spare CR2032 (glucose/ketone meters) and AAA batteries (pump)
    • Spare lancets which will never be used
    • Lip balm for travelling
  • Sick Day Plan
  • Pump Failure Plan
  • A copy of my latest bloodwork
  • Spare pump consumables (the Dexcom G6 applicator is quite bulky otherwise it would also be in there)
  • Spare prescription glasses
  • A small sharps container for travelling (I use an old vitamin bottle)
  • Spare pump belt (I usually wear one and wash one so a spare means I can do this in the hotel room sink)
  • Insulin Saver Bag and Breezy Pack for keeping insulin at temperature when travelling
  • A cartridge of rapid insulin which I rotate out as I refill my pump (room temperature insulin is less likely to cause lipohypertrophy apparently
  • Dot cool Bluetooth temperature monitor (I am not sure if there are still available but it is a great little temperature monitor)
  • Novopen 4 in case I need to MDI my Fiasp cartridges instead of feeding them into my pump
  • Glucagon pen
  • InsulinSaver Temperature monitor: A one-use temperature monitor which I got as a freebie at ATTD and keep in the bag although I have never used them
  • Needles and needle clipper
  • A piece of paper with my name, postal address and phone number on it in case I ever lose the bag

It may seem like a lot of carry but it means I can pick up my bag and go anywhere and I will not need anything for, say, a week. No stressing, no last-minute packing, and ready for work or when I am heading to the airport.

Why You Should Spare a Rose This Valentine’s Day

I have some news: I am now a member of the board for Insulin for Life. It is hard to express my feelings on this because they are many. It is obviously a huge honour to be part of their mission. It is also very daunting. My action or inaction can literally be the difference between people living or dying.

If you are unaware of Insulin for Life they are an Australian-based charity which obtains in-date insulin (either donated or purchased) and related equipment and redistributes it to clinics in disadvantaged countries to be given free to poor people of all ages with diabetes. They have developed collection and distribution centres in eight advantaged countries and provide supplies regularly to clinics in over 30 countries, as well as in response to disasters. They also assist locally led overseas clinics and communities with diabetes screening, education days, and camps for children with diabetes.

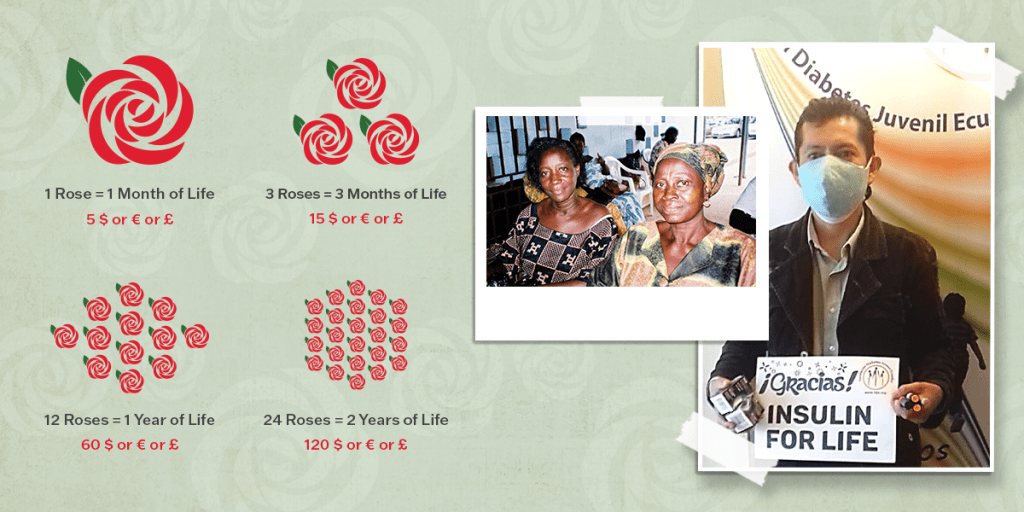
Valentine’s Day is a big part of the year for Insulin for Life because they run the Spare a Rose campaign. This is their major fundraising campaign for the year and was borne out of an idea in the US diabetes community: rather than giving a dozen roses on Valentine’s Day, give one rose and redirect the saved money to Insulin for Life. One rose (about $5) is equivalent to one month of life for someone with type 1 diabetes. If you scrounge some paper from the work office supply cupboard, you could make a paper rose instead and donate the equivalent of all 12 roses and give someone life for a year.

Being a dedoc alumni, I have met people from around the world who are alive because of organisations like Insulin for Life. In some cases, the people I have met have no contemporaries back home with type 1 diabetes because they died without a regular supply of insulin. I have seen the good work Insulin for Life do and believe in their mission so much a dollar of every sale I make through my Etsy store goes directly to them.

If you are interested in helping out, go to the Spare a Rose website to find out more and click the button there to donate. Even if you don’t want to reduce the size of your gift to your loved one or you do not celebrate Valentine’s Day, please consider giving a donation or help promote the campaign on your social channels. It will really help people with type 1 diabetes around the world. Even the smallest assistance could literally save a live.

The campaign is open for all of February. Will you help?

Insulin Cooling Battles: BreezyPacks vs InsulinSaver

My last cooling battle was about four years ago, comparing Frio with BreezyPacks’ Breezy Basic. With a new product on the market, InsulinSaver’s “The Bag”, I thought I would see how the products stack up. To better understand how the BreezyPacks and InsulinSaver bags resist the heating of the insulin pens, check out that last cooling battle link where I explain the role of PCMs and how they work similarly to the Frio but without the soaking.

Disclosures

In the battle, I will be evaluating three cooling bags:

I also have a BreezyPacks bag called the “Breezy Plus” which is the same size as the Basic but with more active material. However, this is no longer on sale at BreezyPacks so I have excluded it from the comparison.

The Breezy Basic (and Plus) I bought at full price online and I bought The Bag at full price while at ATTD2025. I informed BreezyPacks of my intention to do a comparison and I asked if they had data on the Extra or would be willing to provide one for the comparison and they generously sent me one.

Neither BreezyPacks or InsulinSaver are paying me to do this comparison or offering any other incentive.

Comparing the Bags

Website Price (ex. Tax/Shipping)Capacity (Insulin Pens)WeightMax. Temp (C)
Breezy BasicUS$33.903176g41
The BagUS$41.96 (36.90 Euros)6368g54
Breezy ExtraUS$43.9010267g46

In terms of price, the pricing scales with capacity. For shipping to Australia, Breezy is about US$7 and for InsulinSaver it is about US$14.

The weight is a rough indicator of PCM material being used (the substance that resists the change in internal temperature) and we can see The Bag has the most, but it should be noted, we do not know InsulinSaver and BreezyPacks are using the same material. I also weighed my Breezy Plus which came in at 25.1g, similar to the Breezy Extra.

The Bag is also rated for a higher temperature than the Breezys but all fit within the range of most temperatures the bags are likely to be exposed to under normal conditions.

Measuring the Changes in Temperature

To measure the change in temperature, I used my oven on the lowest temperature setting. On the dial this is 50C but, as measured at the end of the experiment, the oven temperature was closer to 36C. This is within the limits of the bags and equivalent to hot summer day here in Sydney, Australia.

As you can see above, the three temperature sensors I used are all measuring the same temperature (this was at the end of the experiment, outside of their bags), within half a degree of each other (about a degree in Fahrenheit).

To replicate the conditions of an insulin pen as closely as possible, I put the probes inside NovoRapid insulin pen containers, retaining the empty glass reservoir inside.

These were then placed in the three bags being tested, one pen per bag.

Finally, these were placed in the oven on the same rack with the fan force function operating to try and maintain as even a temperature as possible.

It was then a case of recording the temperature every 15 minutes until the bags went over 30C or until three hours had passed, whichever came first.

The Results

This result genuinely surprised me. With the additional active material, I expected The Bag temperature to stay flat, relative to the others, but it closely trailed the Breezy Basic. In the final 15 minutes, the Breezy Basic started rising while The Bag was stable and I suspect this was due to all of the active material being liquified and no longer providing protection. Certainly, giving each bag the ‘squeeze test’, the Breezy Basic was almost fully liquefied, the Breezy Extra less so but still containing a fair amount of liquid PCM while The Bag felt almost completely solid. This is either a function of the larger amount of material or confirms InsulinSaver uses a different PCM to BreezyPacks.

I have a hypothesis why the Breezy Basic and The Bag performed similarly while the Breezy Extra heated up quicker and it has to do with the cross-sectional/exposed areas.

The sides of the bags are full of active material, but the ends are not. We can also see the cross-sectional area of the Breezy Extra is about double of The Bag (the top part of the Breezy Extra is also largely unprotected). With possibly less active material than The Bag and a larger unprotected area, this meant the Breezy Extra heated up quicker as the heat came through the unprotected areas. With the smallest cross-section, the Breezy Basic was the best protected from this attack and, even though The Bag’s end area was bigger, this may have been offset by the protection of the additional material on the sides. Ultimately though, after three hours, the Breezy Basic ran out of active material and the temperature started going up.

The good news is, even at these high temperatures/extreme conditions, the Breezy Extra lasted over an hour (and did not go past 31C for three hours), and the other two lasted over three hours.

Conclusions

For the ability to protect, and pen capacity, it is hard to go past The Bag but all three are robust at protecting their contents. For two-week trips, like the one I just did to Europe and the USA, I can see The Bag being used for my backup insulin pens and the Breezy Basic being used for the Fiasp penfills I use to refill my pump. If I need more capacity (or need a bag with a handle) the Breezy Extra is also a great option. I can see myself using the Breezy Extra as a standalone bag with refills, pump sets, backup pens etc. for overnight trips, a bag for work, or day trips.

Product Review: Drew’s Daily Dose Pen Needles

I got offered a box of Drew’s Daily Dose Pen Needles to try from the excellent Ash of Stripped Supply.

I had heard good things so I thought I would give them a go. My disclosures are:

The needles cannot be purchased from Drew’s web site but are purchased through the NDSS.

While I use an insulin pump and do not inject insulin, I do use Ozempic so I used the needles for that. When they ran out, I used the needles that came with Ozempic and a box of BD Ultra-Fine needles. Rather than weekly, I inject a scaled-down dose of Ozempic daily with a new needle, so it was not hard to go through the needle box.

Look and Feel

In the image above we have the Ozempic needle on the left, Drew’s needle in the middle and the BD needle on the right. As you can see, the design of the Ozempic needle and Drew’s needle are a lot similar than the BD needle. Looking at the packaging, the Ozempic needle is a NovoFine Plus 32G 4mm (same gauge and size as the other two needle types). The NovoFine Plus needles can also be purchased through an NDSS order but my understanding is supply can be problematic i.e. nonexistent.

Drew’s Claims

Drew makes a number of claims both on the box and on his web site. This seems like a good place to start the review.

Box Claim: Ergonomic

Ergonomic means “designed for efficiency and comfort in the working environment” which, in this case, presumably means when injecting. Certainly, I found the needles as comfortable on insertion as the other needles I used. Where it was slightly better was on holding the needle in the site for 10 seconds to allow the Ozempic to seep in. It is very easy for the injection pen to move around a little and, generally this did not hurt with the Drew needle, whereas there is sometimes pain with pen movement with the BD needle.

Box Claim: Reliable

I go through the entire box without issue but, then again, I can go through a BD box without issue as well so they perform as well as other needles in this regard.

Box Claim: High Flow

Given I was injecting relatively small amounts, I cannot say this was a major factor in my use. It may be something to consider, though, if you are finding issue with other needle brands.

Box Claim: 3 Bevel

I did not put the needle under the microscope to check but I have no reason to doubt the claim. A bit of Googling suggests NovoFine Plus needles and BD needles are also triple-beveled. Beveling the needle tip (cutting it at an angle) makes for a sharp point and allows the needle to go into the skin more easily.

Website Claim: Flat Hub Technology

It is easier to see what this is referring to if I show another picture without the needle caps on.

As you can see, the NovoFine Plus (Ozempic) needle (left) and Drew’s needle (middle) have a much wider base from which the needle protrudes than the BD needle (right). Based on this, Drew makes a few claims.

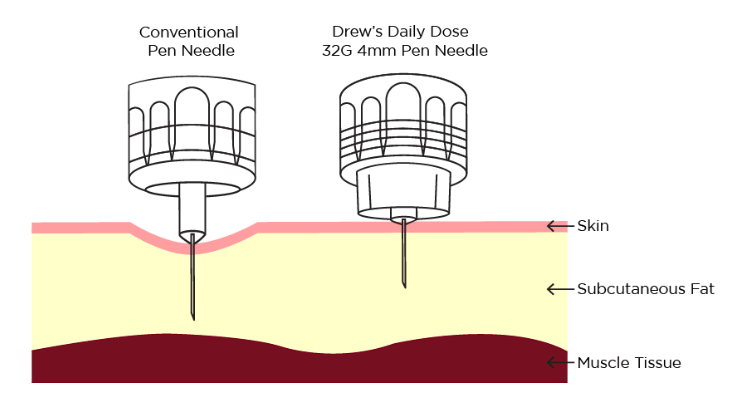
“Reduced Risk of Intra-Muscular Injection”. This is easier to explain with Drew’s diagram than in words.

While the needles may be the same length, the smaller width of the base allows for the skin to be pushed in more with a similar force. This, in turn, may mean the needle penetrates deeper and could hit muscle. Why is this important? Insulin disperses slowly from fat and much quicker from muscle. While generally not recommended, insulin hackers, looking to get a rapid drop in glucose levels, may choose to inject insulin into muscle, rather than fat. For the rest of us this just means less predictability and a higher risk of a hypo.

I did not notice any issue with Ozempic with either needle so I cannot say by how much the design reduces the risk but, again, if this is something you see with your current needle, this may be something to consider.

“Anti-tilt technology”. As I understand it, the idea here is that the wider base limits the pen moving around and reducing the risk of “bending and breakage”. It is true I have had a BD needle bend in site before and I have never had a Drew or NovoFine Plus needle do this. I am wondering if the anti-tilt technology also contributes to the reduced moments of pain, I mentioned earlier, when the pen moved around while the needle was in the injection site.

“Reduces Bruising and Indentation”. The claim is the reduced movement also reduces damage through needle movement, which can lead to bruising and skin distortion. I rarely bruise when injecting (I think this was more common when I first started) so this was not a differentiator for me in considering the different needle brands.

Reduces Needle-Stick Injuries

Again, this is easier to show than describe.

The idea is the green cap can be put into the back to prevent the back of the needle causing a stick injury and the bigger cap protects the front of the needle. Of the three designs, Drew’s is the only one which allows this, although it is a little fiddly. Very handy if you need to inject and you do not have a sharps container at hand.

My Overall Thoughts

The main reason I use the BD needles is because they are often available on the shelf of the chemist and it is a purchase of convenience. However, based on the above, the NovoFine Plus and Drew’s needles have superior aspects and Drew’s is the only one which is its own sharps container. While many of the claimed benefits do not speak strongly to me, this last one does, especially for travel, and for this reason, I will likely order Drew’s needles from now on as part of my NDSS pump supply orders.

If you are interested in getting the 32G*4mm needles for any of the brands mentioned, the NDSS numbers are:

  • NovoFine Plus: 165
  • Drew’s Daily Dose: 338
  • BD Ultrafine: 266

Looping/Automated Insulin Delivery: Does it Work? Commercial vs Open Source, Affordability, and How Professionals Can Support the Lived Experience

I recently presented at the Australian Diabetes Educators Association NSW Branch Conference and wrote an article for the Australian Diabetes Educator journal on looping and how diabetes educators can support people with type 1 diabetes (PWDs) using looping systems, both open source and commercial. This is not a verbatim reproduction of the presentation or the ADEA article but does cover some of the key points which may be useful to PWDs and Health Care Professionals (HCPs). While the focus of the article is the Australian experience, there is value for international audiences as well.

What is Looping?

There are many terms for technologies allowing a Continuous Glucose Monitor (CGM) and an insulin pump to make blood glucose management decisions without the intervention of the PWD. Originally, when such technologies were ‘hacked’ together on the internet, it was referred to as looping. Now, with both open source (internet) and commercial versions available, and recognition in the academic literature, the more formal term Automated Insulin Delivery systems (AIDs) is used. For the rest of the article, this is the term I will use. Similarly, for simplicity, open source/internet systems I will refer to as ‘Open Source’ and commercial systems as ‘Commercial’. There are nuances which are lost in this broad classification but, for the purposes of this article, they are not overly important.

For a brief history of how the internet made the first AID, you can go to my other blog. These days, there are a variety of options for PWDs. In Australia, there are now four main Open Source systems: 

For Commercial systems, at the time of writing, Australia has three commercial looping systems available: 

  • Medtronic 780G + Guardian 4 Sensor 
  • Tandem t:slim X2 with Control IQ + Dexcom G6 
  • YpsoPump with CamAPS FX + Dexcom G6 

Open Source vs Commercial Systems

These days, I use a Commercial system (Ypsopump with CamAPS FX + Dexcom G6) but my first loop was Android APS using both the Libre 2 and Dexcom G6 CGMs and Omnipod pumps. Neither is better than the other but each system has their own features which are more or less appealing to each PWD.

Open Source Commercial 
Built by the wearer/user Commercially available software 
(Generally) The code which it is based on is available for review Proprietary i.e. the code is not available and how it works is often a trade secret
Very ‘tweakable’ Less flexibility/features 
Not formally approved by a government bodyApproved by a government body i.e. the Therapeutic Goods Administration

There is nothing illegal about using an Open Source AID. The lack of government approval means while they cannot be sold commercially, the law in Australia allows the personal use of unapproved medical technologies and devices. This means, while the software code is usually openly available, it is the PWD who must compile it (not as technically challenging as it sounds these days). The advantage of Open Source is that, because it does not have to go through formal approval processes every time a change is made, innovation comes faster with Open Source AIDs.

The advantage of a Commercial system is that it is largely ‘plug and play’. While PWDs need formal training on the use of the CGM and pump, the commercial software is often simpler to use and administer. Some consumers prefer to be hands-on with their technology while others prefer simplicity.

Do AIDs Work and What Are Their Limitations?

AIDs continue to improve but they do have their limitations. While it is possible for a PWD to modify their diet e.g. eat a Low Carb or Very Low Carb diet, and minimise their intervention with the AID, most PWDs will need to bolus for meals and take care during exercise. For tips on dealing with AIDs in exercise, refer to my exercise article.

My experience has been, being a LADA with some residual pancreatic function, I can skip a lot of bolusing and the AID is very good at keeping me in range. These days I bolus for very carby meals (say 45g or more) but do not need to declare/bolus the rest. Everyone’s experience will vary. One thing I never do are bolus corrections. If I do not declare, the AID keeps adding insulin to manage the carbs and automatically manages the ‘landing’, preventing a hypo. If I manually bolus too much, the AID will suspend basal insulin to ‘soak up’ the excess. No corrections means no stacking and while it can be tempting to bring my levels down quicker after a meal, I always try to let the AID do the work. Similarly, whatever my levels are when I go to bed I can, almost without fail, be assured I will wake up in range. As long as my pump has enough insulin and my CGM does not expire, I can be assured a good night’s sleep.

The other great thing about AIDs is they do not stop you from pulling other ‘levers’ in managing diabetes. If you want to eat a very low carb diet with an AID you can. I touch on this in my “Practical Diabetic Solution” article. In short, when the PWD is asleep or otherwise occupied, the AID takes care of glucose management, ensuring superior results compared to relying exclusively on the PWD to make all decisions 24-7.

A criticism sometimes made of AIDs, especially in the Commercial systems, are their high blood glucose targets (the Tandem, for example, does not allow for a target below 6.1mmol/L (110mg/dL)). The truth is not all AIDs are equal. Broadly speaking the Open Source systems allow for a more aggressive target than the Commercial systems but the system with the lowest possible target is the CamAPS system whose target can be made to go as low as 4.4mmol/L (80mg/dL) although I generally set mine to 5.5mmol/L (99mg/dL) as this is the average resting glucose of a person without diabetes.

To the question of how well these systems work, there is now a strong body of evidence that they do and, from a clinical perspective, outperform any other alternative. For example, here are the times in range for the Medtronic system across various regions of the world. As we can see, it is typical to be at least 70% in range (70-180mg/dL) with minimal lows. These results are consistent across the variety of AID systems and, as mentioned before, do not prevent even better results through the use of adjunct therapies such as medications and diet.

How Do People Decide on the Right System for Them?

There are four key factors to consider when choosing an AID:

  • Availability: Are the pump, CGM, phone and related consumables available? 
  • Accessibility: Are the pump, CGM, and phone usable by the individual? 
  • Adaptability: Can the AID system be extended, as desired? 
  • Affordability: Is the AID system affordable? 

In terms of affordability, Australia is unique in being ‘half-pregnant’ with their AID subsidies. For people with type 1 diabetes, CGMs are funded with a small co-payment by the PWD whereas pumps are effectively unfunded. To get an insulin pump, the PWD must either get private health insurance or pay the, say, $8,000 for the pump out of their own pocket. There is a petition urging the Australian government to change this inequity which I encourage you to sign.

For the other factors, considerations include:

  • More choice of glucose targets.: As mentioned, different systems have different target ranges which may be important to some 
  • Readability: For a user with vision impairment, a high-contrast screen or management via a mobile phone may be desirable. 
  • Connectivity to other devices: Being able to access functions via a watch or the internet may be useful. 
  • Form factor: Device size, whether it is tubed or tubeless, and whether it has an IP rating for water resistance can be key decision factors for some wearers

The available combinations are also important as it is likely a PWD is already using a specific CGM and may want to stay with that CGM as part of their AID system. In fact, there are limited combinations available for AIDs.

 Tandem t:slim X2 YpsoPump Omnipod Dash Medtronic 780G 
Dexcom G6 Android/iPhone (CGM only) Android via CamAPS Android/iPhone  
Medtronic Guardian    Samsung/iPhone (Monitor only) 
Abbott Libre 2   Android  

Above we can see the available Open Source and Commercial combinations in the Australian market for pumps and CGMs approved for use in Australia (Green = Commercial, Blue = Open Source). As we can see, for someone using a Libre 2, the only option available is an Open Source one. Similarly, while the next version of the Omnipod has an AID system (approved in Australia but not widely available), the main Omnipod version available in Australia, at the time of writing, does not with the gap being filled, again, with Open Source.

How HCPs Can Help?

There is understandably some nervousness with HCPS about supporting or recommending Open Source systems to PWDs. These are, almost by definition, unofficial/unapproved systems. On the other hand, to stay relevant to a PWDs care, they cannot remove themselves completely and let the internet and social media be a PWD’s only source of information. Thankfully, there is some guidance for HCPs out there.

Locally, guidance is limited. Diabetes Australia has a position statement on “People with type 1 diabetes and Do It Yourself (DIY) technology solutions” but it is over five years old, light on specific guidance and, arguably, out of date. In its statements around commercial systems it suggests “(In Australia) there is no approved product that is a fully closed-loop system”, and “there is currently no subsidy for the CGM component for adults over the age of 21 years”. Both statements are no longer correct.

Internationally, there are three published documents providing guidance to HCPs and applicable to the Australian context. These are:

These documents are comprehensive in their guidance and freely available to view and download at the above links. Their main points are: 

  • While there are legal complications in recommending Open Source systems, users still require support. Therefore, it makes sense for the HCP to learn about these systems to provide effective guidance. 
  • If the HCP is unable to learn and provide guidance, they should collaborate with individuals who can. 

Conclusions

AIDs provide a lot of value to PWDs and both Commercial and Open Source systems are valid options, depending on the PWD’s needs. While they have their limitations, in terms of bolusing and exercise, AIDs are proven to provide benefit in all global settings in terms of time in range and overnight management.

While it can be daunting for an HCP to provide guidance to PWDs using AIDs, especially if it is Open Source, it is important to provide a voice of reason when there can be a variety of information sources which are less informed or reliable. Thankfully, there are multiple peer-reviewed international guides for the HCP to provide precisely the support PWDs need.

Review: CareSens Dual

I was recently asked to present at the NSW Branch Conference for the Australian Diabetes Educators Association (ADEA) on Looping/Automated Insulin Delivery and what it means for Diabetes Educators.

One of the perks of these conferences are the sponsor stands where various companies set up and offer freebies. One such stand was Pharmaco Diabetes with the CareSens Dual.

They actually had a range of glucometers but the Dual piqued my interest as it measures glucose and ketones. I have an Abbott Freestyle Optium Neo which was literally the first glucometer given to me seven years ago at diagnosis so, given its age, I thought road-testing a backup would be a good option.

The folks at Pharmaco were generous enough to send me one to try out so this is how it went.

What I Received

In the package was the meter box, a box of ketone strips, a guide for ketones, and some brochure-ware on the full range of meters and consumables.

One of the meters in the brochure which I thought was great was the CareSens N Voice which can speak the reading and a larger screen for people with visual impairment. This consideration of the user really impressed me.

The meter box came with the usual suspects (see image below). The one thing which surprised me was the logbook. Do PWDs still use a physical logbook? I was using the MySugr app almost from day one. These days I have Nightscout.

The warranty registration was interesting in that it was dual-country. The New Zealand one promised a free gift whereas the Australian one did not. The CareSens is essentially the only fully subsidised glucometer in New Zealand so New Zealand PWDs are very familiar with it. In Australia, if you are registered with the NDSS, you can get a free meter from a variety of manufacturers, including CareSens.

The instructions are pretty much the same for all these kinds of devices so nothing too unusual here. I did get a giggle out of the ‘do not insert the strip the wrong way round’ image. Rather than the lancet which comes with CareSens, if you fingerprick regularly, I recommend a Genteel which allows you to use any part of your palm, rather than the sensitive fingertips. This advice is not specific to CareSens; I am just not a fan of jamming a needle into one of the most sensitive parts of my fingers.

While it is not an issue for me, the glucometer allows you to press a button to eject the strip without touching it, and the same for the lancet in the finger-pricker. I guess there are people out there who feel squeamish about touching their own blood and, in these cases, the meter would be a great choice.

I have not had an opportunity to test for ketones (I do not run ketogenic and have not been near DKA since diagnosis) but the blood testing was within 10% of my CGM, which is good enough for me. I did look for online sources to validate the accuracy of the meter but could find nothing recent.

Conclusions

The meter will be a solid addition to my collection and provide me more than one device which can test for ketones. I am tempted to put one of my dual-sensor meters in my travel luggage so I can ketone test easily while away from home and have the other one easily available for home testing.

Thoughts on the Australian Government’s Inquiry into Diabetes

This week, on the 3rd July, 2024, the Australian government released the 23 recommendations resulting from their Inquiry into Diabetes. This blog will review each recommendation and consider its impact on people living with diabetes, and how the Australian government manages diabetes in general. The blog is quite long, so if you want the short version, head on over to the tl;dr section.

Details of the Inquiry

The Inquiry kicked off back in 24 May, 2023 when the Honorable Mark Butler MP called for a committee to investigate and report on diabetes. The Terms of Reference for the inquiry were, according to the committee’s chair, Doctor Mike Freelander, “very broad” with a view to “get as much information as we can so we can get a plan for the future”. Reading the article, the motivation for the inquiry seemed to be the incidence of obesity and type 2 diabetes in Australia and coincided with the release of a study from Deakin University confirming an increase in the rate of type 2 diabetes in Australia.

This was not an inquiry targeted at type 1 diabetes, but at diabetes in general, with obesity and risk factors also being considered. This is reflected directly in the formal Terms of Reference for the inquiry:

“The Committee will investigate:

  • The causes of diabetes (type 1, type 2 and gestational) in Australia, including risk factors such as genetics, family history, age, physical inactivity, other medical conditions and medications used;
  • New evidence-based advances in the prevention, diagnosis and management of diabetes, in Australia and internationally;
  • The broader impacts of diabetes on Australia’s health system and economy;
  • Any interrelated health issues between diabetes and obesity in Australia, including the relationship between type 2 and gestational diabetes and obesity, the causes of obesity and the evidence-base in the prevention, diagnosis and management of obesity; and
  • The effectiveness of current Australian Government policies and programs to prevent, diagnose and manage diabetes.”

The problem I have with investigating the “interrelated health issues between diabetes and obesity” and “risk factors such as genetics, family history, age, physical inactivity…” is these do not apply to all diabetes types equally, and also apply to other diseases, such as breast cancer. As can also be seen in this last link, risk factors are often conflated with causation. Correlation is not the same as causation and, in the case of diabetes, leads to a lot of unnecessary blame and stigma (there are plenty of skinny type 2s, chubby type 1s, and muggles of both sizes, so broad correlations have limited application at the level of the individual, especially when a proven chain of causality has not been established.)

As it was a public inquiry, submissions and public hearings were part of the process giving a voice, to any interest group who felt the inquiry Terms of Reference related to them, for consideration. So, from the start, there was potential for recommendations which may address broad health issues in the Australian population but not necessarily address prevention of diabetes, treatment of diabetes, or improvements for those living with diabetes. As you will see below, this lack of focus in the Terms of Reference led to a lack of focus in the Recommendations with some having tenuous links to diabetes, at best.

Let us review the recommendations and consider their implications.

The 23 Recommendations

Recommendation 1: The Committee recommends that the Australian Government undertakes a comprehensive economic analysis of the direct and indirect cost of all forms of diabetes mellitus in Australia.

This is an excellent idea. Approval for subsidised medications, equipment, and treatments rely on favourable economic consequences. Approval may require a measure of economic return e.g. spend $1 and return $2 worth of productivity within a specific time period, or an estimation of the cost for ‘Quality-Adjusted Life Years’ (QALYs.) In the case of the NDSS subsidy for CGMs, the cost came in at around $35,000 per QALY, below the unofficial approval threshold of $50,000 per QALY. Subsidies for things like Type 2 CGMs or Type 1 Loops will need to go through a similar exercise. Basically, accurate economic analysis will lower the barriers for smart decisions to be made.

Recommendation 2: The Committee recommends that the National Health and Medical Research Council expedites a review of the Australian Dietary Guidelines, and ensures that the revised guidelines include adequate information for Australians living with diabetes.

Here we see the broader terms of the inquiry coming into play. I do not see a lot coming out of this other than education programmes for ‘guides to healthy eating’. I do not believe information access is the problem. I think we all know we need to move more and eat less, preferably eating food with lower energy density. I can almost guarantee any “adequate information for Australians living with diabetes” will concentrate on type 2 diabetes and its risk factors and largely ignore any other type whose needs are different (people with type 1 are less concerned with glycaemic index/load and more concerned with total carbohydrate count, for example.) The cynic in me has no expectation this level of nuance will be captured in any revisions and expect the guidelines will not go much deeper than “fat bad, protein good, but remember to eat some carbs.”

Recommendation 3: The Committee recommends that the Australian Government implements food labelling reforms targeting added sugar to allow consumers to clearly identify the content of added sugar from front-of-pack labelling. This food labelling initiative should be separate from the information regarding added sugar potentially being included in the Nutrition Information Panel.

This one has little to do with people living with diabetes, whose concerns are carbohydrates in general, rather than just added sugar. I see this adding no value to me personally and see it causing a lot of confusion for people with type 1 diabetes. When bolusing, the need of a person using insulin is for clear carbohydrate labelling. This should not be sacrificed for ‘added sugar’ warnings.

The other concern I have is this recommendation will be seen as ‘proof’ that eating sugar causes diabetes. The causes of diabetes types 1 and 2 are unknown i.e. the reason the immune system starts attacking the pancreas in type 1 is still not understood. Even the proof that sugar causes obesity is limited so, given the Terms of Reference, I think sugar was over-represented in this inquiry.

Recommendation 4: The Committee recommends that the Australian Government implements a levy on sugar-sweetened beverages, such that the price is modelled on international best practice and the anticipated improvement of health outcomes. The levy should be graduated according to the sugar content.

Sugar levies in other countries have shown a decrease in sugar consumption and a slowing of obesity rates in children but that is all the evidence shows so far. While reductions in rates of type 2 diabetes are predicted, using the risk correlations, there has not been enough time to confirm the prediction. I am not against the idea of a sugar tax (my secret hope being it will increase the variety of sugar-free drinks on the supermarket shelves), I am simply uncertain of its place in this inquiry. The hypothesis that sugar consumption leads to weight gain which may lead to an increased rate of obesity which may lead to an increase in the rate of type 2 diabetes seems tenuous to me in its relevance for an inquiry into diabetes of all types.

Recommendation 5: The Committee recommends that the Australian Government considers regulating the marketing and advertising of unhealthy food to children, and that this regulation should:

  • Focus on children defined as those aged 16 and under
  • Be applied to television, radio, gaming and online
  • Use definition of unhealthy food that has been independently developed.

More recommendations relating to general population health with little consideration for diabetes specifically. At least Recommendation 2 threw diabetes in at the end. Again, I am not against lumping in unhealthy food in with cigarettes and alcohol, in terms of advertising, I am simply struggling to link the recommendation to diabetes and the Terms of Reference. My guess is the link is unhealthy food may lead to obesity which increases the risk of type 2 diabetes but I am surprised there were not recommendations raised with a more direct link to diabetes prevention and management. For example, Teplizumab is proven to delay stage 3 type 1 diabetes by literally years so why has it been left out of the recommendations, but an unproven sugar tax included?

Recommendation 6: The Committee recommends that the Australian Government provides its response to the Australian Food Story: Feeding the Nation and Beyond report and considers a dedicated resource within the Department of Health and Aged Care to support access to healthy food to all Australian communities.

For the curious, the referenced report can be found here. The report is focussed on food production and food security but was not about links between food and health. In fact, the word ‘health’ gets mentioned only three times throughout the report’s recommendations. Once in reference to the National Health and Medical Research Council and, of the other two references, the first calls for a National Food Council to advise the government of food matters of which ‘Health and Nutrition’ was one of ten factors to be considered. The second reference called for changes to funding research on ‘food, health and nutrition.’

As we can see, there is a theme here that food, and specifically, sugar is considered the culprit to Australia’s health issues and incidence of diabetes (diabetes type be damned). There is no doubt that access to healthy food is a good thing for Australia in general but, for me, these food recommendations miss the mark for an inquiry on diabetes of all types.

Recommendation 7: The Committee recommends that the Australian Government, in consultation and cooperation with state and territory governments, develops a best practice framework to tackle the problem of obesogenic environments, including through better urban planning and the development of physical activity initiatives and supports efforts to increase access to regular exercise in schools and neighbourhoods as a matter of urgency.

This is a recommendation exclusively considering obesity. The Term of Reference for obesity was “Any interrelated health issues between diabetes and obesity in Australia, including the relationship between type 2 and gestational diabetes and obesity, the causes of obesity and the evidence-base in the prevention, diagnosis and management of obesity.” The recommendation implies that lowering the barriers to physical exercise in urban areas will impact obesity levels. It is a reasonable hypothesis but I could not find a lot of evidence to prove it, similar to the case with sugar leading to obesity and type 2 diabetes. So, again, I question the relevance of this recommendation to this inquiry.

The recommendation is another nice idea for general health improvement but, for tackling how Australia manages diabetes? For me, it seems a poor foundation to build on. Perhaps funding research to work out the causes, rather than acting on the correlations and hoping for the best, would be a better use of money. To mix metaphors, we want to smash the causal chain, not throw stuff at the wall and see what sticks.

Recommendation 8: The Committee recommends that the Australian Government explores the potential for effective national screening programs for all forms of diabetes, particularly Type 2 diabetes.

I appreciate I have not been completely glowing in my appraisal of the recommendations so far but this one strikes me as really ill-conceived. Screening for every type of diabetes except type 2 diabetes makes more sense. For type 1, for example, we recently saw the approval for a national screening program in Italy. So why not type 2? Because there is no simple test to definitively diagnose type 2 diabetes. For type 1 we can test for auto-antibodies (which appear years before symptoms) and for MODY we can conduct genetic testing but, for type 2, the test is the symptoms i.e. elevated blood sugars and their effects on the body. There is literally no test we can conduct on a baby to determine if they are going to get type 2 diabetes and even in adults, diagnosis is a series of tests, not some simple screener.

The best we could do would be to implement regular testing of HbA1c which tells us the person may have some form of diabetes but is certainly not definitive for type 2. An elevated HbA1c, in the absence of a diagnosis of diabetes, is referred to as Pre-Diabetes and it is estimated over 1/3 of the US adult population is pre-diabetic. That is a lot of noise to filter out to find the true type 2 diabetics.

The idea of screening for MODY and type 1 diabetes makes sense to me, assuming it is cost effective (see commentary of Recommendation 1). Screening for MODY makes sense to reduce the widespread misdiagnosis and resulting mistreatment, and screening for type 1 makes sense because immune interventions can delay the onset of symptoms for years. It is clear though, screening only makes sense if something is going to be done with a positive test. Unless medical interventions are part of the overall strategy, screening is useless.

Recommendation 9: The Committee recommends that the Australian Government implements a national public health campaign to increase public awareness of the early signs of all forms of diabetes mellitus.

By the early signs for all forms of diabetes, I assume they mean the “Four T’s” which indicate an insufficient amount of insulin in the blood. Certainly, prior to diagnosis, I had enough awareness of two of the T’s (Toilet and Thirst) to know I needed to see a doctor when I was permanently thirsty and peeing every 30 minutes. Given awareness could prevent DKA death in an undiagnosed type 1, I do have some sympathy for this recommendation, assuming it is cost effective.

Recommendation 10: The Committee recommends that the Australian Government funds the development of education-based obesity screening information and resources.

More obesity recommendations which, again, speak to the health of the general population, rather than at diabetes. As with the screening in Recommendation 8, it only makes sense if there is a resulting intervention strategy for those positively identified. While ‘resources’ suggests some level of funded intervention, it is a bit nebulous.

Recommendation 11: The Committee recommends that the Australian Government implements a national public health campaign to increase awareness of the importance of prevention, identification of early signs, and good management of all forms of diabetes mellitus.

This is similar or, at least, related to Recommendation 9 regarding early signs. Prevention is an interesting one. Again, we are predicating our actions off of correlations, given the causes of diabetes in many of its forms (including type 1 and 2) are unknown. If the cause is unknown, how can we prevent it and raise awareness on what is needed to prevent it? As alluded to earlier, the usual suspects for ‘prevention’ equally apply to other diseases as they do to diabetes.

“Good management”, I assume, means eating less and moving more. I doubt this will include, for example, a national public health campaign on the correct use of insulin or on the importance of a well-rounded health care team.

What this is really recommending is a public health campaign to improve the overall health of Australians.

Recommendation 12: The Committee recommends that equitable access to health care for people living with all forms of diabetes be improved through:

  • Access to longer appointments with a health care provider subsidised by the MBS
  • Access to case conferencing models of health care, especially in rural and remote areas
  • Access to telehealth services
  • Increase in the number of item numbers for allied health consultation for those with diabetes for diabetes educators and dieticians and other allied health providers
  • Access to diabetes educators, including in high-risk outer metropolitan, rural and remote communities.

Finally! A recommendation which actually considers diabetes specifically, rather than being about general population health and issues of sugar consumption, a lack of exercise, and obesity. We are about halfway through the recommendations and, by my reckoning, maybe three of the 12 recommendations are specifically targeted at diabetes, rather than general population health.

Longer appointments are a nice idea if there is something to talk about. I would personally like to see more research and effort being put into structuring the conversations with health care providers so they are more relevant to the person with diabetes (PWD) and deliver real value, rather than being a doctor taking twice as long to tell their client they need to use insulin properly, eat ‘healthier’ carbs, lose weight, and do more exercise. How about a session where the concerns of the PWD are discussed BEFORE the blood results? How about a discussion around the various technologies available and why they may or may not be relevant/desirable to the PWD? How about a discussion of the various medications available which may be of benefit? I am hoping to construct a framework for such a discussion applying corporate motivation theory but this takes time. You can read details of my idea here.

I had to look up “case conferencing” but, from what I can tell, it is health care professional speed dating. Basically, you round up a team of health care professionals (Endo, Dietician, Exercise Physiologist etc.) and have people meet with them as part of a single session. Given the lack of health care professionals in rural areas the organised corralling of them in one spot, and the recommendation for telehealth services make a lot of sense.

Assuming it is done with cultural consideration, I see this having a huge impact in rural aboriginal communities. Aboriginal people are four times more likely to have diabetes/pre-diabetes than their non-indigenous counterparts. Anything that can be done to lower the barriers to health care and education access for these disproportionately affected communities is a good thing.

Then we move on to diabetes educators, a topic of particular interest for me. Firstly, fixing the ‘item numbers’ for allied health professionals is a great idea. A key reason why I do not see my diabetes educator is Medicare and my private health insurance do not recognise the visits. My Diabetes Educator has a Provider Number but, for whatever reason, the visits fall between the cracks. My hope would be that this recommendation would fix that.

Access to diabetes educators (DEs) is a problem in Australia whether it is in urban or rural areas although other HCPs seem to cover the shortfall so that the health of PWDs does not suffer. The online forums constantly buzz with people craving access to a DE but they either do not have one in their area or the DEs are booked out. The pathway to becoming a DE is quite narrow in that you must have a health-related qualification (dietician, nurse etc.) before you can become accredited as a DE.

My personal belief is a person who has lived with diabetes for, say, ten years, could offer tremendous value to someone newly diagnosed but the prospect of studying for three years to obtain a health degree so they can then study to be a DE is a barrier too high for many. A solution might be for a sub-accreditation for non-HCPs where PWDs can assist the newly diagnosed in a structured manner. The pool of available talent would increase and, if managed properly, would not compromise the quality of service given.

Recommendation 13: The Committee recommends that the Australian Government reviews the limits for accessing juvenile mental health and diabetes services, with a view to enabling young people to continue receiving support for longer.

I am unsure which specific programs this relates to, but it sounds like there are specific programs where the recipients ‘age out’, similar to what used to happen with the CGM subsidies when it was limited to people with type 1 diabetes who were 21 years and under. I can see this being particularly important in the case of mental health services where suddenly cutting off the services because of a birthday could be disastrous. This being said, the supply of mental health professionals, such as psychiatrists, is very limited with many having waiting lists stretching for months.

It may also be alluding to the largely useless Insulin Pump Program which subsidises insulin pumps for people with type 1 diabetes under the age of 21. To date, the program has not had a significant impact so broadening the pool of potential recipients would be good.

Recommendation 14: The Committee recommends the Australian Government work with the state and territory governments to develop education tools and resources to support all staff across the health care system to improve understanding of diabetes, its different forms, the early signs and management. The Diabetes in Schools program should be funded to allow all schools to access it.

A high-level but reasonable recommendation. In fact, the NDSS already have the National Diabetes Nursing Education Framework which would go a long way to achieving this goal. The workbook associated to the program is an outstanding resource to give this baseline understanding.

I had to look up the Diabetes in Schools program but it sounds like a great initiative.

Recommendation 15: The Committee recommends that subsidised access to Continuous Glucose Monitors (CGMs) be further expanded. In the first instance, all access limitations in relation to patients with Type 1 diabetes should be removed. Furthermore, individuals with insulin-dependent Type 3c diabetes and patients with gestational diabetes should be made eligible for subsidised CGMs and for those with Type 2 diabetes requiring regular insulin. The Committee recommends prioritising the removal of age limitations on access to subsidised access for Type 1 diabetes patients.

This is a great recommendation. Type 3c diabetes is diabetes caused by physical damage to the pancreas. This may be as a result of an accident, surgery, or perhaps cancer. People with type 3c diabetes often fall through the cracks and have a difficult time accessing subsidy programs despite often having similar needs as people with type 1 diabetes. Expanding access to people with gestational diabetes and insulin-dependent type 2 diabetes also makes sense. This may also open up the door to extending CGM subsidies to the wider type 2 diabetes cohort in the future if evidence shows it is economically viable.

Recommendation 16: The Australian Government should explore expanding subsidised access to insulin pumps for all Australians with Type 1 diabetes. A gradual increase, such as expanding access to those aged 40 and under, would be useful as an initial step.

This is another issue I have strong thoughts on, and I was a co-author on this petition which describes why the current model is broken. I was also a signatory to the recently released Consensus Statement on Automated Insulin Delivery for Type 1 Diabetes in Australia.

A gradual increase makes sense although why it would be based on being less than 40 years of age mystifies me. As far as I know, there is no medical evidence to suggest 40 years has significance in the efficacy of pump use. For me, it would make more sense to roll it out in a manner similar to how the CGM subsidy was rolled out e.g. ((type 1 diabetes AND (21 years and under OR indigenous OR concession card holder)) OR (insulin-dependent gestational diabetes). The rest of us would access a pump in the same way as we do today and, over time, the program could expend where the evidence supports the case.

Recommendation 17: The Committee recommends that the Australian Government undertakes a review of the price and choice of insulin pumps in Australia.

I have no idea where this one is coming from. We have a pretty good choice of pumps in Australia so why fix something which is not broken? I hope this is not suggesting we have too much choice and implies we should go down a path similar to, say, New Zealand where only two pumps are funded. Choice is not a luxury; it ensures people are getting the right technology to maximise their prospect of success. Their job may mean a tubeless pump is a better choice. They may have sight impairment which means a pump which connects to a phone or which has a high-contrast screen is the best option. A wider choice ensures a broader set of people’s needs can be met.

Recommendation 18: The Committee recommends that the Australian Government, subject to a positive recommendation from the Pharmaceutical Benefits Advisory Committee, expands the eligibility criteria for Glucagon-like Peptide-1 (GLP-1) receptor agonists, particularly for high-risk patients.

Yes! A great recommendation. I talked about GLP-1s and their benefits for all types of diabetes around four years ago, based on the results coming out from international conferences. These results are now filtering down to the government subsidy level and, hopefully, will soon lead to wider availability for these powerful tools although, historically, supply has been an issue.

The next generation of GLP-1s are now coming out with even more impressive results in terms of weight loss and glucose management. The most well-known is arguably Tirzepatide (Mounjaro) which is approved for people with type 2 diabetes but not type 1. Upcoming trials hope to show it is of benefit to both types of diabetes.

Recommendation 19: The Committee recommends that the Australian Government establishes mechanisms for securing supplies of Glucagon-like Peptide-1 (GLP-1) receptor agonists for disadvantaged and remote communities, including Aboriginal and Torres Strait Island communities.

As mentioned in Recommendation 18, supply of GLP-1s worldwide has been an issue. Given their benefit for both weight loss and for people with diabetes, it is a good suggestion although it is not clear to me how it is to be implemented. If those of us in the cities are struggling to get supply, and the issue is worldwide, this makes access a non-starter for remote communities whose logistics challenges will only add to the problems.

Recommendation 20: The Committee recommends that the Australian Government considers expanding access to bariatric surgery within the public system for eligible patients.

For people with type 2 diabetes and obesity, bariatric surgery has an impressive remission rate of around 50-95%. In Australia, to be eligible for the surgery you must have a Body-Mass Index (BMI) of over 40, or type 2 diabetes and a BMI of over 35. The recommendation is not clear in which direction access should be expanded (lower BMI? different types of diabetes?) Also, only so many surgeries can be conducted in Australia annually and the government would need to provide significant funding to keep up with the current demand, let alone increased demand.

Recommendation 21: The Committee recommends that the Australian Government takes steps to manage diabetes research efforts through the Australian Centre for Disease Control (CDC) by coordinating with the peak bodies such as JDRF and Diabetes Australia research priorities with an emphasis on equitable access and prevention. The Committee also recommends that the Australian Government considers increased funding for Type 1 diabetes research and clinical trials.

All sensible recommendations. I assume coordination between the relevant bodies is not as efficient as it could be and thus the call for improvement. If it means better use of money to help people with diabetes, I am all for it.

Recommendation 22: The Committee recommends that the Australian Government undertakes a survey of current diabetes-related data, with a view to developing strategies for establishing new and improving current data sources and for establishing a national diabetes mellitus register within the CDC.

This is an interesting one as I thought, until recently, that Australia had pretty good data because of the NDSS diabetes database. However, when the register was first established, ‘best guesses’ were made to the type of diabetes people had, based on the information available at the time. This summary covers the history of the NDSS register and some of the problems in the quality of its data.

To give an idea of how, even today, poor data are being captured, according to the NDSS database there are literally no people with type 1 diabetes in Australia who are insulin independent. This means LADAs who, by definition, do not require insulin for at least six months after diagnosis, are lost in the system. Why is this the case? Because it is really hard to change the details in the NDSS database once a person is registered. This means all LADAs, including myself, are told to register as insulin-dependent so that access to subsidised resources is not an issue later on. In short, there is no formal recognition of LADA in Australia and certainly no data to ascertain the prevalence and characteristics of this type 1 sub-type.

Recommendation 23: The Committee recommends that the Australian Centre for Evaluation in the Department of Treasury commits to the ongoing assessment of any actions taken in respect of Committee recommendations made in this report.

This sounds more like bookkeeping than a specific diabetes-related recommendation. Accountability is good though, so I appreciate the value of it.

tl;dr

The recommendations of the inquiry are a bit of a mixed bag, driven by overly broad Terms of Reference and, arguably, pre-conceived notions on the causes of diabetes and, specifically, type 2 diabetes.

The recommendations fall into the following categories (23 is generic and has been left off):

Sugar Recommendations (3, 4)

In short, added sugar is the devil and should be treated as such (change food labelling to call out sugar has been added and tax it). No argument from me on that front but, for type 1 diabetes, total carbohydrates is the key piece of information. As long as that is not sacrificed, all good. As for a sugar tax, if in encourages more variety in sugar-free drinks, I am all for it.

Why is sugar being mentioned in an inquiry into diabetes? No idea. Sugar is not mentioned in the Terms of Reference and its inclusion will feed misconceptions about diabetes being caused by sugar eating.

Obesity Recommendations (7, 10, 20)

The obesity recommendations (design cities for exercise, screen for obesity, and make bariatric surgery more accessible) do not talk at the links between diabetes and obesity, as outlined in the Terms of Reference and tenuously relate to “the causes of obesity and the evidence-base in the prevention, diagnosis and management of obesity”. I would argue they miss this mark given there is limited evidence that city design improves obesity rates. As for the final two recommendations, without investment in what happens after a positive screening and in bariatric services, all we are doing is creating demand for a system which is not set up to serve it.

General Health Recommendations (2, 5, 6)

In short, review dietary guidelines, regulate the advertising of unhealthy food to children, and ensure access to healthy food. All great ideas, and all as relevant to diabetes as they are to many other diseases where diet is considered a risk factor. Should they be in the recommendations for an inquiry into diabetes? Is there evidence that any of these measures will impact diabetes in the Australian population? Do they align to the specified Terms of Reference? No.

Diabetes Recommendations (1, 8, 9, 11-19, 21, 22)

The remaining two thirds of the recommendations actually relate to diabetes, which is good. Economic rigour around the cost of diabetes is a great idea (1) and provides a foundation for smart, economically responsible decisions. Screening for diabetes (I have no idea why they focus on type 2 diabetes here) and increasing overall awareness to enable ‘self-screening’ (8, 9, 11) makes a lot of sense. Catching diabetes early in all of its forms improves outcomes for the individual and the country.

Improved access to health care professionals (12, 13) for all Australians is a good idea but the shortage of these professionals is not considered in the recommendations and risks straining an already strained system further.

The call for improved education of health care professionals in their knowledge of diabetes (14) is a great idea. Many people with diabetes (especially people with type 1 diabetes) actively avoid engaging with the health system because they know they will need to educate the HCP themselves and, often, their knowledge and experience will not be respected and ignored for a lecture received back in medical school decades earlier. Improved education is a tide which will raise all boats and improve the system for all.

Improved and subsidised access to proven medications and technologies (15, 16, 18, 19) is a great idea although I am concerned about the suggestion to review the choice of pumps (17) unless this is aimed at getting the most recent pumps into the country as Australia is a version behind in many CGM and pump systems. The suggestion to use a cut-off of 40 years of age for pump subsidy confounds me and is misaligned to previous Australian subsidy schemes and pump subsidy schemes being rolled out internationally.

Improved research funding administration and access to data (21, 22), as with Recommendation 1, will only improve the decisions made in the future. We can only set our direction when we know where we are, where we are wanting to get to and the means we have to get there, and while many of the recommendations make good guesses to the direction we should head, Recommendations 1, 21, and 22 enable a foundation for much smarter navigation.

Conclusions

There are some good ideas here but there are also missed opportunities and half-solutions. Screening for different diabetes types and for obesity is well and good but what then? The emergence of immune intervention treatments for type 1 diabetes e.g. Teplizumab is also a missed opportunity and a great solution to the question of screening next steps. The lack of health care professionals to service the diabetes community is also absent from the recommendations despite calls to increase demand.

I look forward to seeing how these recommendations are implemented and hope, the ones which are truly focussed on diabetes get the attention they deserve. Diabetes is a costly disease for both the individual and the country so smart, evidence-based decisions, will make a big difference.